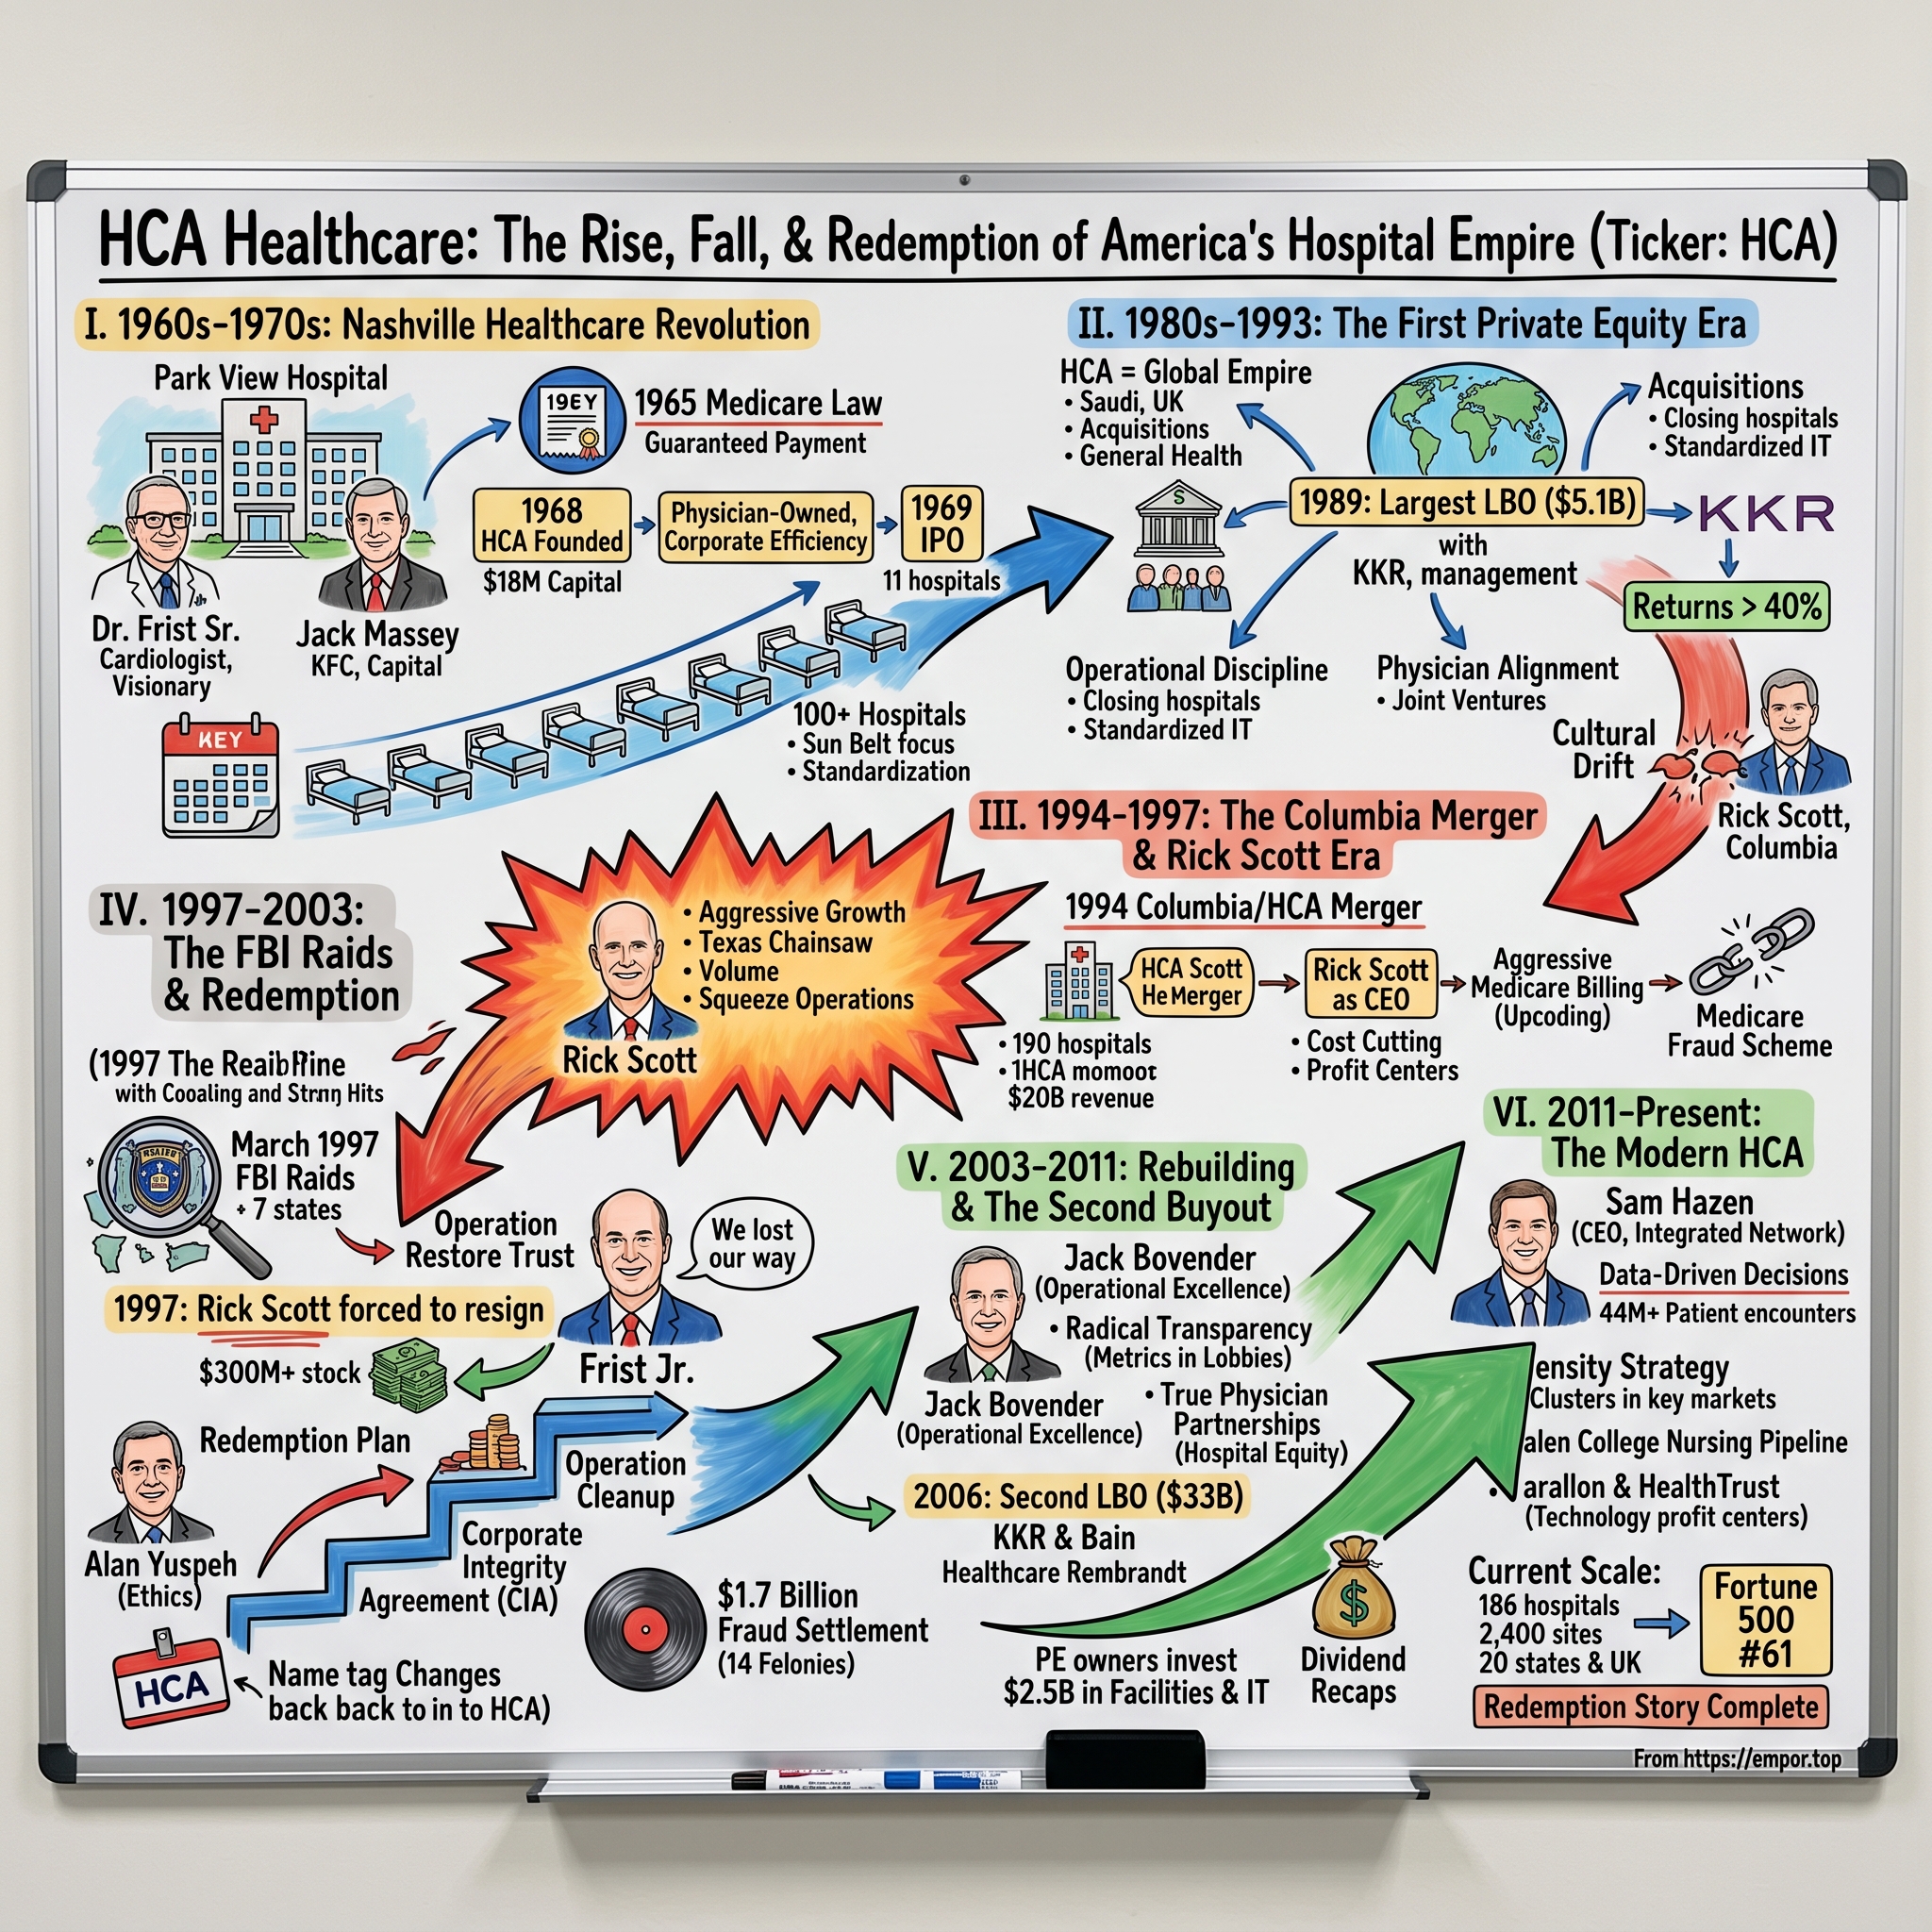
HCA Healthcare: The Scale Machine of American Medicine
I. Introduction & Episode Roadmap (10–15 min)
The Hook: A Hospital System the Size of an Industry
Picture a hospital emergency department at 2 a.m. in suburban Houston. A trauma bay preps for a motorcycle crash, a toddler with a 104-degree fever waits in triage, and upstairs a cardiac surgeon scrubs in for an emergency bypass. Multiply that scene across 190 hospitals, add roughly 2,600 outpatient sites, and distribute them across 19 states and England12. That scale represents HCA Healthcare on any given night.
The operational volume is vast. In 2025, HCA generated $75.6 billion in revenue, earned $6.8 billion of net income attributable to shareholders, and delivered $15.6 billion of Adjusted EBITDA3. Across that single year, its facilities logged nearly 10 million emergency room visits and roughly 2.3 million inpatient admissions2. Its workforce totals approximately 320,000 employees, giving HCA a payroll larger than the population of many American cities2.
Yet HCA does not position itself as a technology company or an asset-light platform. Management describes the organization as a federation of local health systems, each competing market by market for patients, physicians, nurses, and commercial insurance contracts. The central dynamic is that HCA built one of the most durable compounding records in American healthcare by operating a capital-intensive, heavily regulated brick-and-mortar business with rigorous operational discipline.
The Central Paradox
How did a Nashville provider founded by two physicians and the entrepreneur who built Kentucky Fried Chicken into a national chain survive a federal fraud investigation that yielded $1.7 billion in combined criminal and civil recoveries—at the time the largest healthcare fraud recovery in U.S. history4? How did it then execute a roughly $33 billion leveraged buyout, including about $11.7 billion of assumed or refinanced debt5, return to public markets in 20116, and repurchase more than half of its diluted share count over the subsequent fourteen years73?
That trajectory—from federal settlement to private-equity buyout to systematic share-repurchase program—forms the spine of this episode.
The Investment Spine
The bull thesis on HCA rests on local network clustering and disciplined capital allocation. By concentrating acute-care hospitals and outpatient sites in fast-growing Sunbelt metropolitan areas, HCA builds local market share that makes its facilities difficult for commercial insurers to exclude from provider networks. The company runs procurement, revenue-cycle management, and clinical staffing through centralized shared-service platforms, then recycles free cash flow into continuous share repurchases while holding leverage inside a stated target band.
The Counter-Spine
The bear thesis focuses on payer mix and regulatory vulnerability. HCA's operating margins rely heavily on commercially insured patients subsidizing government-reimbursed care, and that commercial profit pool faces ongoing pressure. Medicare Advantage plans now account for more HCA revenue than traditional fee-for-service Medicare2. Enhanced Affordable Care Act subsidies expired at the end of 2025, and HCA's reported data showed that patients losing exchange coverage transitioned to uninsured status at an almost one-for-one rate8. Meanwhile, Medicaid supplemental payments, which contributed approximately $6.2 billion of revenue in 20252, face federal regulatory caps phasing in over the coming years. Combined with the operational friction from its Valesco physician-staffing joint venture and a North Carolina antitrust and quality-commitment lawsuit over the Mission Health acquisition now heading to trial9, the forward outlook is more contested than past share-price performance indicates.
The Roadmap
This analysis examines the Frist-Massey founding and the company's first leveraged buyout; the aggressive Columbia/HCA consolidation era under Rick Scott and the subsequent federal investigation; the 2006 mega-LBO; the microeconomics of a modern acute-care hospital; HCA's geographic moat and its reliance on Certificate of Need laws; the post-pandemic labor shock and HCA's capital commitments to nursing education and physician staffing; the share-buyback model; a 7 Powers and Five Forces competitive assessment; and a bull-versus-bear stress test. The objective is to evaluate which elements of the compounder narrative are supported by operating evidence.
The starting point is a single community hospital in Nashville, where an Air Force physician tested an operating model adapted from retail chain management.
 Subscribe on LinkedIn
II. The Nashville Syndicate & The Hospital Industrial Complex (1968–1993) (25–30 min)
A Flight Surgeon's Idea
In the mid-1960s, Dr. Thomas F. Frist Jr. was stationed at Robins Air Force Base in Georgia, serving two years as a Strategic Air Command flight surgeon during the Vietnam War10. During his service, he focused on a core premise borrowed from chain retail: if corporate chains could achieve economies of scale to build better stores, why could the same commercial logic not build better hospitals10?
His father, Dr. Thomas F. Frist Sr., was a Nashville internist who had helped establish Park View Hospital as a physician-led community hospital1112. The elder Frist served as the cultural anchor for the venture; the company still cites his guiding principle that medical institutions must provide care "with warmth, compassion and dignity for the individual"13.
The third founder supplied the commercial and transactional acumen that neither physician possessed. Jack C. Massey started his career as a pharmacist in Depression-era Nashville, built a wholesale surgical supply business and a retail drugstore chain, and then stepped out of an early retirement to acquire Kentucky Fried Chicken from Colonel Harland Sanders for $2 million in 1964 alongside John Y. Brown Jr.14. The partners transformed a decentralized network of roadside diners into a standardized national chain, selling the enterprise to Heublein several years later for roughly $240 million14. Massey understood franchising, capital markets, and rapid multi-unit rollouts—disciplines he set out to introduce to acute care.
Medicare Changes the Math
The commercial catalyst arrived through federal legislation. Following the creation of Medicare and Medicaid in 1965, the physician-owners at Park View chose to sell their hospital to a dedicated management company rather than continue running operations themselves11. For the first time, tens of millions of elderly and low-income Americans had guaranteed public coverage, backed by initial federal reimbursement formulas that were generous and largely cost-based. A hospital that could secure capital, upgrade equipment, and maintain high occupancy suddenly had an expanding, reliable customer base.
In 1968, the Frists and Massey incorporated Hospital Corporation of America to operate and expand Park View, establishing one of the earliest investor-owned hospital corporations in the country1112. The value proposition pitched to independent community hospitals was direct: centralize purchasing and back-office billing, provide admitting physicians with modern surgical suites and equipment, and rely on a corporate parent to raise capital in public markets.
The IPO and the Roll-Up
Public equity markets immediately embraced the model. When HCA went public in 1969 with 11 facilities, its shares jumped from $18 to $40 on the first day of trading, and by year-end the company had expanded to 26 hospitals with about 3,000 beds12. Annual revenue climbed from roughly $29 million in 1968 to more than $1 billion by 1980, according to company histories summarized in encyclopedic sources11.
By 1979, HCA owned or managed 140 hospitals11. A rapid succession of debt-financed corporate acquisitions followed. In 1980, the company purchased General Health Services and its 14 hospitals. In 1981, it acquired Hospital Affiliates International, which operated 154 facilities, along with Health Care Corporation, creating the foundation of a nationwide psychiatric-hospital network15. Following the Hospital Affiliates International transaction, HCA controlled roughly one-fifth of all privately owned U.S. hospitals15. By the mid-1980s, the enterprise owned more than 200 hospitals and managed an additional 200 under contract11, establishing the template for investor-owned hospital chains.
Too Big, Too Scattered
Rapid expansion, however, created structural vulnerabilities. When the federal government shifted Medicare to fixed prospective payments per diagnosis in the early 1980s, the reimbursement change penalized facilities burdened with high overhead or low patient volume—characteristics typical of many HCA community assets. In 1987, the company spun off 104 of its less profitable, mostly rural hospitals into a newly formed employee-owned entity called HealthTrust, creating what was then the largest employee stock-ownership plan in the country1115. The divestiture served as a pragmatic acknowledgment that accumulating hospital beds was not the same as owning high-performing, high-margin facilities.
Frist Jr., who had become president in 1977 and chairman and CEO in 198710, then restructured the balance sheet more aggressively. In March 1989, management completed a roughly $4.9 billion leveraged buyout to take HCA private, backed by an equity group that included Goldman Sachs, Morgan Guaranty, Rockefeller interests, and Fort Worth investor Richard Rainwater15. To service the buyout debt, HCA divested its hospital-management subsidiary, its clinical laboratory division, and its international holdings15. After streamlining operations outside the quarterly scrutiny of public markets, HCA returned to public exchanges in 1992, restoring the liquid equity currency that positioned it for a subsequent stock merger16.
Rainwater's role in the 1989 syndicate proved pivotal. The same financier who helped capitalize HCA's initial buyout was concurrently funding an upstart rival that would soon absorb it. Furthermore, the transaction demonstrated an enduring corporate playbook: management had used private leverage to reshape the organization away from public markets, an approach it would repeat on a far larger scale in 2006.
What This Era Teaches
The founders' foundational thesis proved accurate: acute-care hospitals capture tangible operational efficiencies through centralized purchasing, pooled capital access, and professionalized administration. Yet the 1987 HealthTrust divestiture proved that those advantages depend on geographic density and clinical acuity rather than sheer facility count. Operating hundreds of dispersed rural facilities created administrative scale without local market power against regional payers. That operational distinction—between absolute footprint size and local market density—became the governing principle for HCA's subsequent consolidation strategy.
HCA's leaner, re-listed organization did not remain independent for long. In Texas, a former healthcare attorney with a far more aggressive approach to market consolidation was already building the vehicle that would acquire it.
III. The Columbia Era, Rick Scott & The $1.7B Medicare Fraud Cataclysm (1994–2003) (30–35 min)
Two Hospitals in El Paso
The Columbia story began in El Paso with an ambitious attorney and a familiar financier. Richard L. "Rick" Scott, a Kansas City native and SMU-trained healthcare lawyer, teamed up with Fort Worth investor Richard Rainwater around 1987–881617. Each contributed $125,000 in equity, purchasing two El Paso hospitals for approximately $60 million, financed almost entirely with bank debt from Citicorp16.
Scott's operating model differed sharply from what the Frists had established in Nashville. Columbia acquired underperforming hospitals, cut overhead costs, and then sold equity stakes to admitting physicians through local limited partnerships; in El Paso, doctors eventually held roughly 40% of the local system16. The commercial logic was straightforward and, in retrospect, legally hazardous: physicians who held an equity stake in the facility had a direct financial incentive to admit their patients there.
The Mega-Mergers
Columbia expanded through rapid, debt-fueled acquisitions. In 1993, it agreed to merge with Galen Health Care, the hospital operator spun out of Humana, in a stock swap valued at about $3.2 billion that expanded its footprint to 94 hospitals16. Then, in February 1994, Columbia merged with HCA in a roughly $5.7 billion stock transaction, creating a company with $10 billion in annual revenue and operations across 26 states1611. Frist Jr. became chairman; Scott stayed on as chief executive officer16.
In October 1994, Columbia/HCA agreed to acquire Healthtrust—the same company HCA had spun off to an ESOP in 1987—for about $5.6 billion, completing the transaction in April 199516. By the time Scott departed in 1997, Columbia/HCA had expanded into an empire of more than 340 hospitals, 135 surgery centers, and 550 home-health locations across 37 states and two foreign countries, staffed by more than 285,000 employees17.
The Culture Clash
The rapid roll-up forced two fundamentally different corporate cultures into a single boardroom. Frist's Nashville version of HCA had developed around physician co-leadership and an institutional pace13. Scott's Columbia was built on aggressive dealmaking, strict cost reductions, and physician equity partnerships16. The Galen merger alone had made Columbia the largest non-governmental hospital chain in the country, and each subsequent deal enlarged that lead16. Yet federal investigators would soon allege that behind the rapid growth was a deliberate system engineered to maximize government reimbursement at national scale.
March 1997: The Raids
In March 1997, federal agents raided Columbia/HCA facilities in El Paso, launching an inquiry that expanded across multiple states in the months that followed1117. The investigation examined whether the company had systematically defrauded Medicare and Medicaid.
The allegations the government ultimately settled were wide-ranging: false cost reports, billing for unallowable expenses, inflated claims for indigent care, improper cost allocations, false claims tied to wound-care centers and non-covered drugs, and kickbacks paid to physicians in exchange for patient referrals4. In effect, investigators charged that the company had converted clinical billing and reimbursement mechanics into an aggressive corporate profit center.
The board moved quickly. Scott resigned as chairman and CEO in July 1997, less than four months after the investigation became public, and Frist Jr. returned to lead the company on July 24, 19971711. Scott was never indicted17.
The Reckoning
Resolving the criminal and civil liabilities took six years. In December 2000, Columbia/HCA agreed to pay $840 million in criminal fines and civil damages, and pleaded guilty to at least 14 corporate felonies, including conspiracy to defraud the United States17. The company also signed a corporate integrity agreement11.
In June 2003, the Justice Department announced the final civil resolution: $631 million in civil penalties and damages, plus a separate $250 million administrative settlement with CMS and $17.5 million to state Medicaid programs4. The Justice Department described the combined $1.7 billion as the largest recovery it had ever reached in a healthcare fraud investigation, and it paid whistleblowers about $151.6 million, then the highest combined qui tam award ever paid4.
Myth vs. Reality: "HCA Fixed Its Culture for Good"
A common retrospective narrative holds that the scandal forced HCA to construct an industry-leading compliance architecture, and that the company has operated as a corporate model citizen ever since. The verifiable record shows that the company operated under a corporate integrity agreement11, sold off numerous hospitals, surgery centers, and home-care operations beginning in 1998, and renamed itself HCA – The Healthcare Company in 200018. What cannot be verified from public filings is the claim that its compliance systems represent the industry's "gold standard"; that remains an organizational characterization rather than an auditable fact.
The more grounded conclusion is narrower. The fraud investigation proved that for a business funded largely by public programs, billing integrity is integral to enterprise value rather than a routine back-office function. The crisis also established a permanent institutional memory: HCA's subsequent generation of leaders came of age in its aftermath, and the company's later controversies, most notably at Mission Health, have centered on clinical service levels and contractual commitments rather than systematic billing fraud. That shift marks a meaningful operational distinction, not an exoneration.
Having survived its reckoning with the federal government, HCA soon faced mounting pressure from public equity markets. Within three years of the final settlement, management would take the company private again, this time at a transaction scale no leveraged buyout had ever reached.
IV. The Mega-LBO & The Bain/KKR Operational Crucible (2006–2011) (25–30 min)
A Summer Deal
In July 2006, HCA announced an agreement to sell itself to an investor consortium comprising Bain Capital, Kohlberg Kravis Roberts & Co., Merrill Lynch Global Private Equity, and the Frist family, alongside corporate management519. Under the transaction terms, public shareholders received $51 per share in cash, valuing the buyout at roughly $33 billion, including approximately $11.7 billion of assumed or refinanced debt5. The transaction closed on November 17, 2006, at which point HCA operated 172 acute-care hospitals and 95 freestanding surgery centers across 21 states, England, and Switzerland under Chairman and Chief Executive Officer Jack O. Bovender Jr.5. The transaction eclipsed RJR Nabisco as the largest leveraged buyout in corporate history up to that time19.
Management pursued the take-private transaction against a backdrop of slowing inpatient admission growth and escalating bad-debt expense from uninsured patients. Public equity markets had grown impatient with multi-year hospital turnaround cycles. Operating as a privately held company shielded executive leadership and private-equity sponsors from quarterly earnings scrutiny, while the interest expense generated by the buyout debt created a substantial tax shield that supported the transaction's financial structure.
The Balance Sheet Transformation
The scale of the transaction fundamentally altered HCA's capital structure. At the close of 2005, HCA carried roughly $10.5 billion in total debt; by the end of 2010, that obligation had expanded to about $28.2 billion20. Over the same five-year span, annual revenue grew from about $24.5 billion to $30.7 billion20. To capitalize the buyout, the sponsor group had injected an initial equity commitment of approximately $5.3 billion20.
In operational terms, the company nearly tripled its debt burden while expanding top-line revenue by roughly one-quarter. Sustaining that debt load required highly predictable operating cash flows, demonstrating to credit markets that acute-care hospital systems—despite significant regulatory and political exposure—generated utility-like cash flows that could support substantial fixed debt obligations.
The Operating Playbook
While conventional narratives attributed the operational improvements during this period primarily to private-equity ownership, HCA's internal operating executives executed a strategic realignment designed to leverage local market density.
Three primary levers shaped the operating turnaround. First, capital expenditures were concentrated into high-acuity service lines—such as cardiology, oncology, orthopedics, and trauma—within metropolitan regions where HCA already held leading market share. Second, administrative and back-office functions were aggressively centralized; the company later formalized these shared-service capabilities by establishing Parallon for revenue-cycle and administrative operations, while deploying HealthTrust as its shared-service supply-chain and procurement engine13. Third, commercial managed-care contracting became tightly coordinated, allowing HCA to negotiate with regional and national health plans as a consolidated network rather than through fragmented local facilities.
Because HCA does not break out the standalone financial contribution of each operational lever, attributing the financial return of the buyout to any single initiative remains speculative. The observable result was a more focused, heavily leveraged hospital network that expanded annual revenue and consistently converted operating earnings into free cash flow.
Getting Paid Before the Exit
Before returning to public equity markets, the sponsor syndicate executed a series of debt-financed dividend recapitalizations, borrowing against HCA's balance sheet to pay special cash dividends that returned the majority of their initial equity capital20.
These dividend distributions transferred balance-sheet risk from the private-equity sponsors to creditors and the underlying hospital operating entity. The recapitalizations proved lucrative because operating cash flows remained durable through the 2008 financial crisis, though they would have created severe financial distress had the system encountered a prolonged volume downturn or an unexpected federal reimbursement reduction.
The Return to the NYSE
On March 10, 2011, HCA completed its return to public equity markets, listing its common stock on the New York Stock Exchange after pricing its initial public offering at $30 per share6. The offering comprised 126.2 million shares—approximately 87.7 million primary shares sold by the company and 38.5 million secondary shares sold by existing shareholders—raising gross proceeds of roughly $3.8 billion prior to the underwriters' over-allotment option6. Management designated the company's net proceeds from the offering to pay down outstanding debt6.
The enterprise that returned to public exchanges retained a heavily leveraged balance sheet. At year-end 2011, HCA carried approximately $27.1 billion in total debt across a footprint of 163 hospitals7. Diluted earnings per share reached $4.97 in 2011, though that figure reflected a $1.5 billion gain associated with acquiring a controlling interest in the HealthONE joint venture in Denver; adjusting for one-time and non-operating items, diluted EPS stood at $2.857. Furthermore, management immediately resumed what would become its primary capital deployment strategy, repurchasing roughly $1.5 billion of common stock during 2011 alone7.
What the Buyout Proved
The 2006 leveraged buyout demonstrated that HCA's hospital network could generate cash flows sufficient to service substantial debt obligations throughout a severe macroeconomic downturn. However, that performance did not establish that high leverage is without systemic trade-offs. The lasting structural legacy of the buyout is visible across two fronts: a balance sheet engineered to operate with tens of billions of dollars in permanent debt, and a Frist-family ownership stake that steadily increased on a percentage basis as the company systematically repurchased shares from public investors.
Evaluating why institutional lenders accepted that leverage profile—and how the operating system generates sustained cash flow—requires examining the underlying unit economics of the modern acute-care hospital.
V. The Anatomy of Modern Acute Care: Segments, Payers, and Unit Economics (35–40 min)
Inside the Hospital P&L
Imagine two patients arriving at the same HCA emergency room in Dallas on the same night with the same chest pain. Both get the same cardiac workup, the same stent and the same two-night stay. One is covered by an employer plan through a large bank; the other is on traditional Medicare. The hospital's cost of treating them is nearly identical. What the hospital gets paid is not. That gap is the single most important fact about hospital economics.
How HCA Reports Itself
HCA reports as a single business but manages its hospitals through geographic groups, currently the National, American and Atlantic groups2. It does not report separate profit figures for inpatient and outpatient care, but it does disclose that outpatient revenue accounted for about 38% of patient revenues in 2025, 2024 and 20232. That steadiness is worth pausing on: despite years of talk about care migrating out of hospitals, HCA's own mix has barely moved, partly because the company counts many of its outpatient sites inside the hospital network.
The Volume Metrics, in Plain English
Four metrics tell most of the story.
Admissions are the number of people checked into a hospital bed. In 2025, HCA admitted about 2.3 million patients2.
Equivalent admissions try to capture outpatient activity in the same unit. HCA calculates them by multiplying admissions by the ratio of total gross revenue to gross inpatient revenue2. A simple analogy is a restaurant that converts takeout sales into "equivalent dine-in covers" so that total activity can be compared year to year. In 2025, HCA reported about 4.1 million equivalent admissions2.
Same-facility versions of these figures strip out hospitals bought or sold, showing organic demand. Same-facility equivalent admissions rose 2.4% in 20253 and 2.7% in the second quarter of 20261.
Revenue per equivalent admission combines price, acuity and payer mix into one number. It rose 4.1% in 20253 and 6.4% in the second quarter of 2026, though the latter was inflated by a large Florida Medicaid payment18.
Three more operating numbers round out the picture. Patients stayed an average of 4.8 days in 2025, down slightly from 4.9 days in 2023; HCA's hospitals ran at 73% occupancy; and it took about 51 days on average to collect a dollar of revenue, an improvement from 54 days a year earlier2. Each of these is a quiet productivity lever. Shaving a fraction of a day off the average stay across more than two million admissions frees thousands of bed-days, which is the equivalent of building capacity without pouring concrete. Faster collections free cash that can be spent on buybacks or equipment. These are not glamorous numbers, but they are where a hospital operator's process advantage actually shows up.
Case mix index, a measure of how sick and resource-intensive patients are, is a related concept: a hospital doing more open-heart surgery and fewer routine medical admissions will see its case mix rise, and with it, revenue per patient. HCA discusses acuity on calls but does not publish a single enterprise-wide index figure in its quarterly releases, so investors see acuity mostly through revenue per equivalent admission.
The Payer Mix: The Economic Truth
In 2025, HCA derived 48.9% of revenue from private insurers and managed care plans, 14.9% from traditional Medicare, 17.8% from managed Medicare (Medicare Advantage), 7.8% from Medicaid, 4.9% from managed Medicaid, 2.5% from international operations, and 3.2% from other sources including the uninsured2. Put more simply, Medicare and Medicaid programs together accounted for 45.4% of revenue2.
Now compare that to patient counts. Managed care and other insurers accounted for only about 32% of HCA's admissions in 2025, while uninsured patients accounted for about 7%2. Roughly one-third of the patients generate roughly half the revenue. HCA's 10-K states the mechanism plainly: private payers "typically reimburse health care providers at a higher rate" than Medicare, Medicaid or self-pay patients2.
This is the cross-subsidy at the heart of American hospitals. Commercial patients pay well above cost; government programs pay closer to cost, or below it; the uninsured often pay little or nothing. A hospital's margin depends less on how many patients it treats than on which patients they are.
The Hidden Pillar: Supplemental Payments
There is a second, less visible source of support. HCA's revenue from Medicaid state-directed and supplemental payment programs totaled about $6.2 billion in 2025, up from $5.5 billion in 20242. For context, HCA's pre-tax income in 2025 was about $9.8 billion2. Those programs are not pure profit; many are funded by provider taxes that HCA itself pays, which is why HCA's other operating expenses rise when the programs grow8. But they are material enough that changes to them move the whole company's earnings.
The One Big Beautiful Bill Act, which HCA's filings refer to as the 2025 Federal Budget Act, tightens both sides of this machine. It prohibits states from establishing new provider taxes or raising existing ones for state fiscal years beginning on or after October 1, 2026, and, starting in 2028, grandfathered state-directed payment arrangements will be reduced by 10 percentage points annually until they reach the new allowable limits2. These are not hypothetical risks. They are scheduled.
The Cost Stack
On the other side of the ledger, the 2025 cost structure looked like this: salaries and benefits consumed 43.5% of revenue, supplies 15.0%, other operating expenses 21.0%, depreciation and amortization 4.6%, and interest 3.0%, leaving pre-tax income at 13.0% of revenue2. Labor is the single largest line and the most volatile, as 2022 would prove.
The lesson from these numbers is operating leverage. Because labor and buildings are largely fixed in the short run, a few points of revenue growth above cost inflation drop disproportionately to profit, and a few points of shortfall hurt disproportionately. HCA's financial reputation rests on managing that seesaw better than its peers.
Historical Falsification: Does Scale Protect HCA from the Payer Squeeze?
The bull claim is that HCA's scale insulates it from pricing pressure. The evidence partly supports that claim and partly rejects it.
In its favor: revenue per equivalent admission has kept rising, and HCA has reported steady commercial rate increases in its calls. Against it: Medicare Advantage, which pays at roughly Medicare-like rates while using commercial-style tools such as prior authorization and claim denials, now contributes more revenue than traditional Medicare2. And in 2026, the most important payer-mix event was not negotiated at all. When enhanced ACA premium tax credits expired at the end of 2025, HCA's exchange admissions fell 15% in both the first and second quarters, and management found that those patients "migrated almost one for one to uninsured"8. The company originally guided to a $600 million to $900 million hit to 2026 Adjusted EBITDA from exchanges21; by July, that estimate had grown to $1.0 billion to $1.2 billion8.
The conclusion is that scale gives HCA leverage against individual insurers, but not against policy. The payer squeeze that matters most is political, and no amount of local density can negotiate with Congress. The claim survives in a narrower form: HCA wins price negotiations with commercial plans, but its margin is hostage to the size of the commercially insured and exchange-covered population in its states.
That leads naturally to the question of why commercial insurers keep paying HCA's prices at all, which is where geography comes in.
VI. The Geographic Moat: Certificate of Need (CON), Payer Leverage, and Local Density (30–35 min)
The Map Is the Strategy
Plotting every HCA hospital on a map reveals an unmistakable geographic clustering. The facilities concentrate heavily in Florida and Texas, with secondary clusters across Tennessee, Georgia, Virginia, the Carolinas, Colorado, Utah, and Nevada. HCA's annual report states the concentration plainly: "Our facilities are heavily concentrated in Florida and Texas," which leaves the company exposed to economic, demographic, and regulatory developments in those two states2. On the second-quarter 2026 earnings call, CEO Sam Hazen identified Florida, Texas, Utah, Nevada, South Carolina, Georgia, and Tennessee as core states targeted for continued expansion8.
This footprint reflects what management terms its market density doctrine. Rather than building a thin national presence, HCA aims to become indispensable across a select group of fast-growing Sunbelt and western metropolitan areas. Because the company does not publish a consolidated, enterprise-wide market-share figure, investors must gauge the depth of its local positioning through regional market data and executive commentary.
The Hub-and-Spoke Network
Operationally, HCA organizes each local market as a hub-and-spoke network. At the center sits a full-service acute-care hospital equipped with trauma bays, advanced cardiac suites, and intensive-care capacity—capital-intensive capabilities that few community rivals can easily replicate. Radiating outward from the central hub are outpatient spokes: freestanding emergency rooms, urgent-care clinics, ambulatory surgery centers, imaging facilities, and physician practices. HCA describes these outpatient sites as "an integral component" of its strategy to build comprehensive local networks2. At the close of 2025, the system operated 121 freestanding ambulatory surgery centers and 31 endoscopy centers, alongside its broader outpatient footprint2.
The economic purpose of this network architecture is patient interception and clinical routing. Outpatient spokes capture patients closer to home, retaining lower-acuity, high-margin procedures in lower-cost settings while funneling complex, capital-intensive cases back to the central inpatient hub. On the second-quarter 2026 earnings call, Hazen reported that HCA operated approximately 5% more sites of care than it had a year earlier, with another 250 to 300 outpatient facilities active in its development or acquisition pipeline8. Over a longer horizon, Hazen noted that enterprise inpatient capacity had expanded from roughly 37,000 beds in 2018 to about 42,000 beds by mid-2026, while system-wide occupancy rose from 71% to 75% over the same period8. HCA expanded its licensed bed count while filling those additional beds at an accelerating rate—a clear operational indicator of underlying demand across its core metropolitan markets.
Certificate of Need: A Weaker Moat Than Advertised
State Certificate of Need (CON) laws require healthcare providers to secure regulatory approval before constructing new facilities or adding specified clinical services. Because they restrict new entrants, CON regimes are often cited by equity analysts as a primary regulatory barrier protecting HCA's hospital franchises. HCA's annual report explicitly acknowledges operating in "a number of states with CON laws" and cautions that repealing them "could reduce barriers to entry and increase competition"2.
Yet the thesis that regulatory franchising underpins HCA's competitive advantage collides with statutory reality: HCA's two largest operating states maintain no hospital CON protections. Texas eliminated its CON program decades ago, repealing it by 1990 at the latest22. Florida enacted statutory reforms that abolished CON review for general acute-care hospitals and new tertiary clinical services effective July 1, 2019, followed by specialty hospitals effective July 1, 202123.
This legislative landscape reshapes the competitive analysis. Across the metropolitan markets that generate the substantial majority of HCA's operating income, competing health systems and surgical operators face no statutory barrier to constructing rival inpatient facilities. HCA's competitive defense in these core territories rests on capital scale, clinical referral networks, ambulatory breadth, and development speed rather than state-granted monopolies. While CON rules remain a meaningful barrier to entry in states like North Carolina and Virginia, characterizing statutory permitting as the bedrock of HCA's enterprise moat overstates its significance. In Texas and Florida, the moat is financial and operational, not regulatory.
Why Insurers Pay: The "Must-Have" Network
The most defensible element of HCA's local franchise is contractual. When a commercial health insurer designs a provider network for corporate employers across Dallas-Fort Worth, Houston, Tampa, or Nashville, the plan must offer geographic coverage and essential service lines that prospective members demand: Level I or II trauma centers, pediatric emergency rooms, comprehensive stroke units, and advanced neonatal intensive care. If HCA commands a decisive share of those critical facilities across a metropolitan area, an insurer cannot market a commercially viable network that excludes HCA.
That market leverage underpins HCA's ability to secure contractual reimbursement increases from commercial managed-care payers on a predictable annual cycle. The financial evidence is indirect but consistent: revenue per equivalent admission has climbed steadily, while commercial managed care has maintained a stable revenue share of roughly 49% across three consecutive reporting years2. What remains unobservable in public filings is the precise pricing premium HCA commands over regional nonprofit peers, as well as the frequency with which the company serves termination notices during contract negotiations.
Historical Falsification: Mission Health
The clearest test of HCA's acquisition playbook unfolded in Asheville, North Carolina.
On February 1, 2019, HCA completed its roughly $1.5 billion purchase of Mission Health, a six-hospital nonprofit system in western North Carolina, bringing HCA to 185 hospitals24. The transaction included explicit contractual commitments: required capital investments, construction of a replacement hospital in Franklin, development of a new behavioral-health facility, adoption of HCA's charity-care policy, and assurances that designated clinical service lines would be maintained24. Net proceeds from the transaction funded the establishment of Dogwood Health Trust, a major regional grantmaking foundation24.
What followed tested every assumption behind the transaction. In December 2023, then-North Carolina Attorney General Josh Stein sued HCA, alleging that the company had breached its asset purchase agreement by degrading emergency and oncology services—clinical lines HCA had contractually agreed not to discontinue for a 10-year period2526. Since the 2019 acquisition, CMS has cited Mission Hospital for "immediate jeopardy"—its most severe deficiency classification, indicating conditions that place patient safety at risk—four times, most recently in January 20269.
In court filings, HCA advanced a strictly textual contractual defense, arguing that only the outright elimination of a clinical service constituted a breach, rather than a reduction in staffing levels, service capacity, or care quality26. On July 28, 2026, North Carolina Business Court Judge Julianna Theall Earp denied cross-motions for summary judgment from HCA and North Carolina Attorney General Jeff Jackson, ruling that both parties had presented reasonable interpretations of the contractual phrase "shall not discontinue" and ordering the case to proceed to trial269. In the same ruling, the court declined to exclude testimony from a state healthcare expert who concluded that an emergency department could not operate under Mission's staffing formulas while maintaining adequate clinical care9.
HCA secured a parallel legal victory in federal antitrust litigation. On September 8, 2026, in a private antitrust class action alleging that HCA and Mission leveraged monopoly market power to impose anticompetitive contracting terms on regional health insurers, Judge Mark A. Davis denied class certification, ruling that the plaintiffs had failed to establish class-wide injury through common proof27.
The Verdict on the Moat
Synthesizing the evidence, HCA's geographic moat remains durable, but its parameters are narrower than the uncritical bull thesis asserts. The economic moat is most defensible where HCA has built deep local market density organically across expanding Sunbelt metros, surrounding tertiary hospital hubs with convenient outpatient assets. Conversely, the model faces friction when HCA acquires a legacy regional nonprofit monopoly and applies standardized staffing and operational cost controls under the watchful eyes of community stakeholders and state regulators. The Mission Health litigation does not invalidate HCA's operating strategy; rather, it underscores the legal, political, and reputational frictions that emerge when corporate discipline is applied to a sole regional provider. The benchmark that will validate or recalibrate this moat thesis is the resolution of the North Carolina trial and any operational or clinical remedies imposed on Mission's operating practices, alongside whether future nonprofit acquisitions face stricter regulatory enforcement mechanisms.
Yet even the densest healthcare network functions only if an operator can adequately staff its facilities with nurses and physicians. In 2021 and 2022, that foundational assumption was tested by a historic labor shock.
VII. The Labor Crisis & The Backward Integration Gambit: Travel Nurses, Galen College & Valesco (35–40 min)
The Travel Nurse Shock
In early 2022, a staffing manager at a busy Florida hospital could log into an agency portal and watch billing rates escalate week by week. Nurses exhausted by two years of pandemic surges had left bedside roles or signed on with third-party staffing agencies offering multiples of standard hospital wages. Health systems faced an immediate operational squeeze: beds were occupied, patient acuity was elevated, and the only alternative to paying agency premiums was taking clinical units offline.
HCA experienced the disruption immediately. In the first quarter of 2022, contract workers accounted for about 11% of its total nursing hours, pushing salaries and benefits up 10% year over year28. Management had projected that labor inflation would moderate as pandemic case counts receded. Instead, premium labor expenses intensified. On April 22, 2022, the company lowered its full-year revenue guidance to $59.5 billion to $61.5 billion and reduced its earnings outlook28. "We now believe improvement in our labor costs will be slower than originally anticipated," Hazen acknowledged on the call28. Analysts at Cowen observed that guidance cuts were exceptionally rare for HCA28.
The Recovery
What followed was a sustained operational normalization. By the third quarter of 2023, contract labor costs had declined 12.5% compared to the prior-year period, while year-to-date contract labor expense dropped 18%, representing a reduction of more than $300 million29. By the fourth quarter of 2025, contract labor expense had subsided to approximately 4.2% of salaries, wages, and benefits, a level management characterized as its normalized operating run rate21. Over the same timeframe, salaries and benefits as a percentage of revenue receded from 45.4% in 2023 to 43.5% in 20252.
The takeaway is not that HCA operates insulated from clinical labor shocks; the 2022 guidance reduction demonstrated that it does not. Rather, the recovery demonstrated that the company's centralized administrative apparatus and recruiting scale enabled it to re-establish margin control faster than many regional nonprofit competitors, which remained burdened by elevated agency labor costs across multiple operating cycles.
Backward Integration: Galen College of Nursing
HCA's strategic initiative to mitigate nursing shortages predated the pandemic. In January 2020, the company acquired a majority equity stake in Galen College of Nursing30. Galen administers practical nursing, associate, bachelor's, master's, and doctoral degree tracks, operating more than two dozen campus locations across approximately a dozen states, frequently co-located adjacent to HCA hospital campuses30. Eligible HCA employees can access up to $5,250 annually in tax-free tuition reimbursement for their coursework30.
The corporate logic represents classic backward integration: convert clinical recruitment from an unpredictable open-market procurement problem into an integrated internal training pipeline. Co-locating nursing education beside acute-care facilities provides an immediate site for required clinical rotations, which naturally feed into postgraduate job offers and long-term staff retention. Hazen has frequently highlighted rising Galen enrollment as evidence of a stabilizing internal nursing pipeline29.
Yet this initiative illustrates the operational gap between institutional capacity and measurable economic return. HCA does not publicly report how many Galen alumni it hires each year, their median employment tenure, or the net dollar volume of contract agency labor the school's graduates have displaced; neither the 2025 Form 10-K nor Galen's corporate partnership materials disclose those metrics230. While the thesis that captive education structurally reduces enterprise labor costs remains plausible, it lacks auditable confirmation. Verifying the return on this educational integration will require disclosed placement and retention statistics, or sustained insulation of labor margins during the next cyclical surge in hospital demand.
The Physician Problem
Clinical staffing pressures were not confined to bedside nursing. The federal No Surprises Act, which took effect in January 2022, restricted out-of-network physicians from balance-billing patients for the spread between provider charges and insurer reimbursements. For outsourced private-equity-backed emergency and anesthesia groups, the statutory change eliminated a primary revenue source. Deprived of balance billing, contracted physician practices sought to recoup lost margins by demanding substantial operating subsidies from the hospital systems they served. On the third-quarter 2023 earnings call, HCA management reported that professional fees paid to contracted providers had surged roughly 20% year to date29.
The Valesco Move
To stabilize coverage across critical service lines, HCA intervened directly in its contracted provider network. The company had long operated a physician-staffing joint venture with EmCare, which later became part of Envision Healthcare. In April 2023, as Envision headed toward bankruptcy under the weight of debt and reimbursement declines, HCA expanded its ownership stake in the joint venture, Valesco Physician Services, from 50% to 90%31. Hazen described the transaction as a "strategically imperative" intervention to protect hospital operating capacity and local competitive positioning29. The acquired venture encompassed approximately 5,000 clinicians providing coverage across roughly 200 hospital programs29.
Historical Falsification: The Valesco Earnings Shock
The immediate financial outcome tested whether HCA's centralized operating model could absorb complex physician-practice economics without dilution. The third-quarter 2023 financial results demonstrated that it could not.
On October 24, 2023, then-Chief Financial Officer Bill Rutherford disclosed that Valesco had reduced Adjusted EBITDA by approximately $100 million during the quarter, projecting ongoing operating losses of about $50 million per quarter for the near term2932. Rutherford explained that physician-billing collections were clearing at significantly lower reimbursement rates than underwriting had assumed as claims adjudicated, acknowledging that the company had been "operating, you know, maybe on some incomplete historical data"29. With Valesco generating roughly $380 million in year-to-date revenue, the disclosures implied an operating unit running at approximately $200 million in quarterly revenue against $250 million in expenses29. Third-quarter diluted earnings per share came in at $3.91, missing Wall Street consensus estimates and prompting management to trim full-year financial guidance32.
The subsequent analyst conference call was unusually sharp. Justin Lake of Wolfe Research remarked that he had rarely witnessed an acquisition miss financial projections by that scale and pressed management to clarify what initial underwriting had miscalculated versus operational realities29. Cal Sternick of J.P. Morgan questioned the duration of the operational drag and whether standard cost restructuring could eliminate the deficit29. Management provided transparent explanations regarding collection shortfalls but offered limited visibility into when profitability would normalize.
Rather than divesting or scaling back the operation, HCA consolidated control. In June 2024, the company acquired the remaining equity to take 100% ownership, subsequently reporting that it had "fully integrated Valesco"31. Following that integration, HCA ceased reporting Valesco's standalone operating results. However, broader physician cost headwinds persisted; on the fourth-quarter 2025 earnings call, management guided that physician professional fee expenses were projected to grow in the "high single digits" throughout 202621.
The operational record refutes the notion that HCA can absorb outsourced clinical practices at cost-neutral terms. Instead, it supports a more pragmatic conclusion: leadership determined that securing guaranteed emergency room and anesthesia coverage was an operational prerequisite to keep its hospital beds and surgical suites generating cash flow, even if that coverage required an internal subsidy. Determining the financial efficacy of that decision requires weighing an unobservable counterfactual—the market subsidies independent physician groups would have demanded during Envision's insolvency. What remains observable in SEC filings is that professional physician fees remain an ongoing cost pressure.
What This Section Says About Management
The post-pandemic labor cycle highlights the boundaries of HCA's operating playbook. When addressing quantifiable hospital-level bottlenecks like contract agency nursing, the company deployed its centralized purchasing and scheduling discipline to compress costs rapidly. Yet when management ventured into out-of-network physician reimbursement dynamics reshaped by federal legislation, underwriting miscalculated collection rates and produced an immediate quarterly earnings shock. That contrast provides a grounded framework for evaluating future capital deployment into non-acute or ancillary clinical services.
While the quarterly EBITDA impact of Valesco was manageable relative to HCA's multi-billion-dollar cash flow, the episode raised a fundamental question for public markets: if even disciplined hospital operators encounter underwriting blind spots when integrating adjacent assets, what governs the company's broader capital allocation? The answer lies in how HCA directs its operating cash flow—most notably through one of the most aggressive and consistent share-repurchase programs in corporate America.
VIII. Capital Allocation Masterclass: The Leveraged Buyback Machine & M&A Benchmarking (25–30 min)
The Operator-in-Chief
That capital allocation strategy is directed by an executive leadership team whose background is rooted in hospital floor operations rather than financial engineering. On quarterly earnings calls, Chief Executive Officer Sam Hazen focuses primarily on operational metrics: emergency room door-to-provider times, inpatient bed occupancy, and elective surgical scheduling channels, answering questions with granular operational detail.
Hazen became CEO on January 1, 2019, after roughly 36 years with the company, having served as president and chief operating officer, Western Group president and Western Group CFO33. Earlier in his career, he held finance roles at Humana and at Galen Health Care, the Humana spinoff that merged with Columbia in the 1990s2. On the July 2026 call he noted that he had been with the company for 43 years8. His career trajectory spans every major era of HCA's corporate formation.
His CFO, Mike Marks, reflects a similar internal background. Marks joined HCA in 1996 and held roles including CFO of the National Group and of the West Florida division before succeeding Bill Rutherford as CFO on May 1, 202434. This executive bench reflects an organization governed by operational continuity.
Corporate governance remains anchored by the founding family. Thomas F. Frist III, son of the co-founder, became board chairman in April 201933. At that time, the family owned about 20% of HCA's shares33. By January 31, 2026, Frist-affiliated investors held approximately 31%, and a stockholders' agreement grants them the right to nominate directors235. That expanded ownership percentage did not stem from substantial open-market purchases by the family; rather, it rose mechanically as HCA repurchased shares from other holders.
The Capital Allocation Formula
HCA's capital allocation follows a consistent pattern. In 2025, it generated $12.6 billion of operating cash flow, spent $4.9 billion on capital expenditures, repurchased $10.1 billion of stock, and paid about $679 million in dividends321. The board authorized a new $10 billion buyback in January 2026 and raised the quarterly dividend from $0.72 to $0.78 per share21.
The pattern continued into 2026. In the second quarter alone, HCA repurchased about 4.75 million shares for $2.06 billion, leaving $7.21 billion of authorization1. Management said it plans to complete most of the existing authorization during the year8.
However, quarterly cash flow timing demonstrates how that capital cadence interacts with operating volatility. Second-quarter 2026 operating cash flow was $2.3 billion, down 45% from a year earlier, which management attributed mainly to the timing of Florida's Medicaid supplemental payment program and to the prior-year deferral of federal tax payments8. In the same quarter, buybacks and dividends together were close to that cash flow, and capital spending added another $1.2 billion8. Timing effects historically reverse over full annual cycles, and HCA's full-year cash generation has historically covered its commitments. But a quarter in which repurchases run at roughly the pace of operating cash flow, while debt rises, shows how much the buyback cadence leans on the balance sheet when cash receipts are lumpy.
Leverage is the other half of the formula. HCA has described its target range as 3x to 4x debt-to-Adjusted EBITDA and has said it is operating in the lower half of that range298. In absolute terms, total debt rose from about $46.5 billion at the end of 2025 to about $49.7 billion by June 30, 202631. Interest expense was about $2.2 billion in 20252.
What the Buybacks Achieved
The cumulative effect on per-share metrics has been substantial. HCA's diluted weighted-average share count was about 496 million in 20117; its 2025 net income and diluted EPS imply a count of roughly 240 million3. The company has retired more than half of its shares in fourteen years. Over the same period, revenue rose roughly two and a half times, from $29.7 billion in 2011 to $75.6 billion in 2025, while diluted EPS rose from $4.97 (or $2.85 excluding one-time gains) to $28.3373.
That arithmetic represents the core mechanism of the HCA compounding story. Moderate revenue growth, stable margins and steady leverage, combined with aggressive share reduction, turned mid-single-digit business growth into double-digit per-share growth.
The Activist's Critique
A critical investor examination identifies three structural vulnerabilities.
First, buybacks funded partly with debt are only as good as the price paid. HCA repurchased stock at around $434 per share in the second quarter of 20261, far above the $30 IPO price. If long-run earnings growth slows, today's repurchases will earn far lower returns than the ones made a decade ago.
Second, rising debt amid policy headwinds carries risk. HCA's leverage ratio is steady because EBITDA has grown, but absolute debt keeps climbing, and the company's EBITDA faces scheduled pressure from Medicaid supplemental payment limits and exchange attrition. If EBITDA flattens, the same debt load looks heavier.
Third, buybacks steadily concentrate control. The Frist block's rise from about 20% to about 31% is a direct consequence of repurchases332. Family ownership arguably aligns the board with long-term owners, but it also reduces the influence of other shareholders over governance questions like executive pay or acquisitions.
None of these points makes the strategy wrong. They define what would make it wrong: a sustained EBITDA decline while debt is at record levels.
M&A Benchmarking: Where Discipline Held and Where It Did Not
HCA's record on acquisitions is mixed in instructive ways. The 2011 HealthONE consolidation, which delivered a large accounting gain, shows the company's preference for buying out partners in markets it already knows7. Mission Health, as covered earlier, looked cheap at about $1.5 billion but carried contractual commitments that are now in litigation2426. Valesco was a defensive acquisition that lost money29.
Peer comparison adds context. Tenet Healthcare took the opposite road. In 2024 it divested 14 hospitals for proceeds of nearly $5 billion and doubled down on its USPI ambulatory surgery platform, which held interests in 518 surgery centers at year-end36. HCA, by contrast, is investing more than $7 billion over the next three years in beds, new hospitals and outpatient sites, betting that owning the full continuum from ER to operating room gives it more bargaining power than an ambulatory pure-play8. Both strategies can work; the market has at times rewarded Tenet's ambulatory tilt. HCA's bet is that the hub still matters.
The conclusion: HCA's capital allocation is disciplined in its core loop of reinvest, repurchase and hold leverage steady, and less consistent at the edges, where diversification and nonprofit acquisitions produced real problems. Calling it a "masterclass" fits the buyback record. It fits the edges less well.
With the capital engine understood, the question becomes whether HCA's competitive position is strong enough to keep feeding it.
IX. The 7 Powers & Porter's 5 Forces: HCA's Competitive Architecture (25–30 min)
A War-Game Setup
Consider a nonprofit health system's board meeting in Tampa evaluating whether to construct a new patient tower five miles from an HCA facility. The system's chief financial officer outlines the competitive imbalance: HCA can outspend the independent hospital on advanced medical technology, recruit specialists through national physician networks, and secure equipment and supply pricing no single-market operator can match. The regional nonprofit counters with local philanthropy, community loyalty, and a tax-exempt operating structure.
That boardroom dynamic frames HCA's competitive architecture. In acute care, rivalry does not pit national corporate platforms against each other across the country. It unfolds metro by metro as a localized war of attrition against regional health systems.
Hamilton Helmer's 7 Powers
Scale Economies (strong). HCA distributes substantial fixed investments—covering enterprise information technology, centralized revenue-cycle operations, supply-chain procurement, and clinical data analytics—across 190 hospitals and roughly 2,600 sites of care1. The system's proprietary Sepsis Prediction and Optimization Therapy (SPOT) algorithm illustrates the economic advantage: developed using clinical data from 31 million patient episodes and deployed across the network, HCA credited the surveillance tool with helping save an estimated 8,000 lives over five years37. A standalone regional hospital cannot amortize software development or data engineering across a comparable patient volume, giving HCA a meaningful unit-cost advantage in operational technology.
Switching Costs (strong for commercial insurers, weak for individual patients). Individual patients face minimal structural friction switching between local hospitals for elective care. Commercial health plans, by contrast, encounter steep switching costs. In Sunbelt metropolitan areas where HCA controls key trauma centers, pediatric emergency departments, and cardiac facilities, excluding the system's hospitals renders an insurer's provider network unmarketable to major regional employers. That contractual indispensability locks in managed-care participation on favorable terms.
Cornered Resource (moderate, narrower than advertised). While regulatory Certificate of Need franchises restrict new capacity in select states, HCA's two largest operating states offer no statutory shield: Texas eliminated hospital CON requirements decades ago, and Florida repealed acute-care CON mandates in 20192223. Instead, HCA's genuine cornered resources are operational and geographic: state-designated Level I and II trauma accreditations, exclusive residency teaching consortiums, established admitting-physician relationships, and irreplaceable suburban real estate acquired ahead of Sunbelt population booms.
Process Power (strong, but domain-specific). HCA's capacity to normalize clinical staffing after the 2022 labor shock faster than nonprofit rivals, while sustaining system-wide hospital occupancy at 75%8, reflects decades of institutionalized operational routines in patient throughput, emergency triage, and bed scheduling. However, this process power has clear organizational boundaries: it proved non-transferable when management attempted to manage outsourced emergency and anesthesia physician billing at Valesco, where initial underwriting and collection processes faltered.
Network Effects (weak, purely local). Acute-care delivery generates no national two-sided network effects; a hospital bed in Denver creates no direct utility for a patient in Nashville. At the metropolitan level, HCA operates a localized referral loop: freestanding urgent-care centers, diagnostic clinics, and affiliated physician practices channel surgical candidates and inpatient admissions into central tertiary hubs. Yet this mechanism functions as hub-and-spoke clinical routing rather than a true self-reinforcing network effect.
Counter-Positioning (moderate). As an investor-owned corporation, HCA can optimize clinical service lines, close underperforming programs, and reallocate capital toward high-acuity surgical specialties far more aggressively than regional nonprofit health systems governed by civic charters and community boards. While this commercial flexibility delivers higher capital efficiency, it simultaneously creates regulatory and public-relations friction, as demonstrated by the litigation over service reductions following the Mission Health acquisition in North Carolina.
Branding (weak). Consumer brand affinity plays a secondary role in acute care, where patients largely select facilities based on physician referrals, emergency proximity, and in-network insurance status. Specialized clinical brands, such as the Sarah Cannon Research Institute—established in 2004 to conduct early-phase clinical trials in oncology13—provide recognized prestige in cancer care, but enterprise branding remains a secondary driver of commercial volume across general acute-care operations.
The takeaway: HCA's structural power derives primarily from scale economies and local payer switching costs, reinforced by operational process power. Cornered resources and branding serve as secondary supports.
Porter's Five Forces
Buyer power (high and rising). The purchasers of hospital care are concentrated commercial health insurers and government agencies. Commercial payers exert continuous scrutiny over clinical claims and prior authorizations, amplified by the expansion of Medicare Advantage. Meanwhile, federal and state programs exercise statutory price-setting authority over approximately 45% of HCA's net revenue through Medicare and Medicaid2, leaving the system exposed to unilateral rate adjustments and statutory budget constraints.
Supplier power (high for labor, moderate for supplies). Clinical staff wield significant pricing leverage during periods of workforce scarcity. The contract travel-nurse surge of 202228 and the escalated professional fee subsidies demanded by contracted physician practices in 202329 demonstrated that specialized clinical labor can compress operating margins rapidly. Conversely, supplier power among medical device manufacturers and pharmaceutical suppliers is held in check by HCA's purchasing scale through its HealthTrust group purchasing organization.
Threat of substitutes (moderate). Clinical substitution emerges via ambulatory surgical migration, home-based health services, and breakthrough pharmacological therapies that eliminate the need for surgical intervention. When asked about the potential volume impact of GLP-1 receptor agonists in 2023, Hazen remarked that it was "way too early" to evaluate long-term trends and observed that bariatric procedures represented less than 0.5% of HCA's total revenue29. Furthermore, HCA's reported patient revenue mix has maintained a steady 38% outpatient share across multiple years2, indicating that the system's expansive network of ambulatory surgery and endoscopy centers has internalized outpatient migration rather than ceding procedures to non-hospital competitors.
Threat of new entrants (low to moderate). Developing a greenfield tertiary hospital requires hundreds of millions of dollars in capital commitments, specialized clinical staffing, and multi-year construction timelines. However, because statutory Certificate of Need barriers no longer restrict general acute-care construction in Florida and Texas, well-capitalized regional nonprofit systems and competing investor-owned operators can and do build rival facilities directly in HCA's core growth corridors, elevating local capital intensity.
Competitive rivalry (intense, local). Hospital competition occurs locally within distinct metropolitan markets, pitting HCA against well-resourced academic medical centers, tax-exempt regional health networks, and investor-owned peers like Tenet Healthcare and Universal Health Services. Evaluating that competitive landscape in July 2026, Hazen characterized HCA's market positioning as "stable to growing" across most geographies, while acknowledging that market share in certain operating divisions remained flat or experienced modest declines8.
The Verdict
Evaluating HCA through these analytical frameworks reveals that its competitive durability rests on a specific triad: scale economies in corporate overhead, high switching costs for regional health plans, and disciplined process power in bed and labor management. Yet the countervailing forces pressing against the system—primarily unilateral government purchasing power and structural clinical labor shortages—are permanent institutional realities rather than transient headwinds. Those pressures explain why HCA's operating margins remain bounded within a predictable range rather than expanding continuously with top-line growth. The moat successfully defends the core franchise, but it cannot insulate the balance sheet from statutory reimbursement shifts.
That balance between operational control and policy vulnerability frames the strategic lessons HCA provides for the broader healthcare industry.
X. Playbook: Business & Investing Lessons (20–25 min)
Lesson 1: Density Beats Dispersion
HCA's 1987 restructuring marked a retreat from geographic dispersion11. Its modern strategy inverted that model, concentrating facilities into fast-growing metropolitan clusters with Florida and Texas at the center2. The strategic takeaway for multi-unit physical operations is that local market share, rather than absolute national footprint, dictates commercial pricing leverage. A regional operator with commanding local density often negotiates from greater strength than a national chain with dispersed outposts.
Yet concentration creates symmetrical exposure. The same regulatory filing that details HCA's local market density notes that operational concentration in Florida and Texas exposes the system to state-specific regulatory actions, severe weather, and regional economic shifts2. Because both states declined to expand Medicaid under the Affordable Care Act2, the 2026 individual exchange disruption exerted an outsized impact across HCA's core footprint. Density generates commercial pricing power, but it trades away geographic diversification—a balance equity investors must evaluate on both sides.
Lesson 2: Cannibalize Yourself Before Someone Else Does
When ambulatory surgery began siphoning volume from inpatient operating suites, HCA acquired and developed freestanding surgery centers rather than defending legacy hospital walls. By year-end 2025, the company operated 121 freestanding ambulatory surgery centers2. On the second-quarter 2026 earnings call, Hazen reported that the ambulatory surgery division expanded earnings through the first half of the year even as elective surgical volumes softened elsewhere, supported by rising clinical acuity across those outpatient suites8. Developing the substitute protected the broader enterprise profit pool.
The strategic principle applies across asset-heavy incumbents confronting lower-cost delivery channels: patient and customer migration is inevitable, making internal ownership of the destination the critical objective. HCA's durable 38% outpatient share of patient revenues indicates that the company has largely absorbed procedural migration within its own network rather than ceding cases to independent operators2. The boundary of that success, however, is scale. Tenet Healthcare's United Surgical Partners International platform, which held interests in 518 ambulatory surgery centers at the end of 2024, operates a substantially larger dedicated outpatient footprint36. HCA's ambulatory strategy functions as an operational defense of its hospital hubs rather than a standalone market-dominant platform.
Lesson 3: Integrate Backward Only Where You Understand the Business
Galen College of Nursing and Valesco Physician Services represented parallel efforts to secure clinical labor choke points through backward vertical integration. Yet their operational execution diverged sharply. Galen aligned with HCA's institutional strengths in physical facility management and clinical training, even if the precise economic return on that captive educational pipeline remains undisclosed in company filings. By contrast, acquiring full control of Valesco forced HCA to manage complex out-of-network physician billing and payer dispute resolutions—an operational discipline where initial underwriting proved flawed and generated immediate quarterly operating losses29. The strategic takeaway is not that backward integration is inherently advantageous, but that vertical integration succeeds only when an operator's established process capabilities directly transfer to the acquired asset.
Lesson 4: Buybacks Compound Only If the Base Holds
HCA's share-repurchase program transformed mid-single-digit top-line expansion into double-digit per-share growth, retiring more than half of the company's diluted share count between 2011 and 202573. However, that capital flywheel depends entirely on the stability of underlying operating cash flow. When executive management lowered full-year 2026 financial guidance following the expiration of enhanced ACA subsidies, the revision underscored how rapidly legislative and regulatory policy can compress the earnings base8. Debt-financed share repurchases mechanically magnify per-share outcomes across both operational expansions and earnings contractions.
Lesson 5: Roll-Ups Die by Their Accounting
The Columbia/HCA consolidation era stands as corporate healthcare's definitive cautionary tale. When enterprise growth leaned on aggressive coding practices and financial incentives for physician admissions, the regulatory resolution culminated in multiple corporate felony guilty pleas and $1.7 billion in combined civil and criminal recoveries417. For any acquisitive roll-up operating within publicly funded programs, reimbursement integrity forms an integral component of enterprise value rather than an incidental compliance detail.
The more nuanced dimension of this history involves institutional incentives. Columbia's local physician partnerships were originally structured to bind admitting doctors to local facilities, but they ultimately incentivized volume generation at the expense of federal healthcare programs. Modern equivalents are more sophisticated, yet the structural tensions persist: automated revenue-cycle tools, clinical coding optimization, and artificial-intelligence-assisted documentation continually operate near the boundary between compliant reimbursement capture and systematic billing inflation. As HCA deploys artificial intelligence more deeply across its revenue-cycle and administrative workflows21, the historical record demonstrates why institutional investors must evaluate billing inquiries and regulatory scrutiny as structural financial risks rather than routine operational background noise.
Lesson 6: Leverage Is a Tool, Not a Strategy
HCA deployed aggressive financial leverage across three distinct eras to transform its corporate structure: the 1989 leveraged buyout, the 2006 mega-LBO, and the systematic post-2011 share-repurchase program1557. Each restructuring succeeded because the underlying hospital operations generated predictable, utility-like operating cash flows that serviced fixed debt obligations. The broader capital-allocation lesson is that financial leverage amplifies an existing operational advantage; it cannot manufacture one. Corporate failures that emulate this playbook typically occur when management teams borrow to retire equity while the underlying cash-generation engine is already deteriorating.
These operational and financial principles set up the final test: whether HCA's compounding engine can withstand the structural pressures now gathering against it.
XI. Bull vs. Bear Case & The Skeptical Investor Stress-Test (25–30 min)
The Stress Test
The payer denial machine. Whether Medicare Advantage plans are structurally squeezing hospital margins is no longer an abstract concern. At HCA, Medicare Advantage revenue now exceeds receipts from traditional fee-for-service Medicare2. In addition, Chief Executive Officer Sam Hazen pointed to a Medicare inpatient rule change that shifted select surgical cases into outpatient settings, where HCA captures some, but not all, of the displaced volume8. That shift introduces administrative friction and payment denials, though it has generated operational drag rather than a margin collapse.
The GLP-1 question. Whether GLP-1 weight-loss medications will diminish long-term demand for cardiac, orthopedic, and diabetes-related inpatient procedures over the next decade remains an open clinical question. Management noted in 2023 that it was too early to judge the structural impact, and operating data has shown no near-term disruption: HCA logged 19 consecutive quarters of volume expansion through year-end 20252921. The multi-year clinical trajectory, however, remains unproven.
The balance sheet. With total debt approaching $50 billion at mid-20261, debt servicing and refinancing rates represent a substantial fixed claim on cash flow. Net interest expense absorbed approximately 3% of revenue in 20252. Because the company's debt-to-Adjusted EBITDA ratio sits comfortably in the lower half of its 3x to 4x target range8, leverage remains manageable under steady operating conditions—though it leaves little cushion if cash flow contracts.
The policy cliff. Federal policy presents the most immediate structural threat. The attrition of individual exchange enrollees following the expiration of enhanced subsidies is projected to reduce 2026 Adjusted EBITDA by $1.0 billion to $1.2 billion8. Compounding that pressure, the federal freeze prohibiting states from establishing new provider taxes or expanding existing ones takes effect in October 2026, followed in 2028 by annual 10-percentage-point reductions to grandfathered state-directed payment programs2. Medicaid supplemental and directed payments contributed approximately $6.2 billion of revenue in 20252. Management has not published a multi-year financial estimate for these phase-downs, leaving investors unable to quantify the net earnings drag.
The Bull Case
Demographics. An aging domestic population provides steady baseline demand for acute care. Hazen told investors in 2023 that aging baby boomers and the prevalence of chronic health conditions anchor structural inpatient utilization29. Reflecting those tailwinds, HCA's long-term operating model underwrites annual volume expansion of 2% to 3%218.
Sunbelt migration. Population inflows into HCA's core Sunbelt corridors continue to outpace national averages. On the July 2026 earnings call, Hazen observed that demographic momentum across the company's operating footprint was "as positive or more positive" than during the initial pandemic migration into the Southeast and Southwest8. To absorb that incoming volume, HCA is deploying more than $7 billion in capital expenditures over three years into new hospital beds, facilities, and outpatient access points8.
Operating leverage from resiliency programs. Management is relying on enterprise-wide efficiency initiatives to protect operating margins. The company's "financial resiliency" program integrates artificial intelligence across revenue-cycle management and supply-chain logistics, while centralizing shared services and global support capabilities to bend the cost curve821. The initial operational traction was visible in the second quarter of 2026, when same-facility operating expense per equivalent admission remained essentially flat year over year after adjusting for Medicaid supplemental payment accounting8.
Capital return durability. Cash conversion supports ongoing shareholder returns. HCA generated $12.6 billion in cash flow from operations in 2025, and carried roughly $7.2 billion in remaining share-repurchase authorization as of mid-202631, sustaining the capital allocation engine that has systematically retired its equity base for more than a decade.
The Bear Case
Uninsured growth. The expiration of enhanced ACA tax credits demonstrated how quickly payer mix can deteriorate. Patients losing exchange coverage transitioned almost entirely into uninsured self-pay status, outpacing internal projections and compelling management to lower full-year financial guidance8. Because Texas and Florida have declined to expand Medicaid under the ACA2, no state safety net exists to cushion the revenue loss across HCA's largest markets.
Supplemental payment dependency. Medicaid state-directed and supplemental payments generated approximately $6.2 billion in revenue in 20252. The scheduled federal phase-downs and provider-tax restrictions established under federal budget legislation represent statutory constraints that cannot be mitigated through commercial payer negotiations or local market leverage.
Regulatory and legal backlash. Litigation over service reductions following the Mission Health acquisition in North Carolina is pending trial9. Concurrently, the statutory repeal of Certificate of Need mandates in Florida and Texas eliminates regulatory barriers to entry, enabling rival health systems and surgical operators to construct competing facilities unhindered by state franchising rules2322.
Physician costs. Clinical staffing headwinds continue to shift toward contracted providers. Executive leadership guided that physician professional fee expenses would increase in the high single digits throughout 202621, while Valesco's standalone operating profitability remains undisclosed following its full corporate absorption.
Elective surgery weakness. High-margin surgical volumes are showing signs of consumer fatigue. Same-facility elective inpatient surgical cases declined 6% year to date through mid-2026, following a 2% contraction in 2025, reflecting a mix of individual exchange attrition and broader patient affordability pressures8.
The Activist's Checklist: Disclosure and Guidance
An activist investor or short-seller evaluating HCA would likely focus on two structural vulnerabilities beyond the headline numbers: disclosure opacity and guidance predictability.
The first issue is disclosure. HCA does not break out Valesco's standalone operating performance following its full buyout, does not report graduate hiring or clinical retention statistics for Galen College of Nursing, and does not publish consolidated, enterprise-wide market-share figures23031. In each instance, leadership asks public shareholders to underwrite strategic capital deployment without an auditable operational scoreboard. For an organization celebrated for granular tracking of patient volumes and room turnover, those omissions are conspicuous.
The second vulnerability centers on forecasting reliability. Wall Street has long regarded HCA's financial guidance as conservative and dependable, and over extended periods that reputation has held. Yet the operating record over the past five years includes three notable downward revisions: an April 2022 reduction caused by the contract nurse wage shock28, an October 2023 guidance cut triggered by Valesco underwriting shortfalls32, and a July 2026 reduction prompted by exchange attrition that exceeded executive models8. Each episode stemmed from a distinct external or strategic shock, and in each case management provided transparent explanations rather than deflecting responsibility. That candor represents an institutional strength. However, the pattern also confirms that the forecasting model is most fragile precisely where future headwinds are concentrated: clinical labor inflation, physician practice economics, and federal healthcare policy.
Management's disclosures on recent earnings calls have at least provided granular post-mortems. When pressed in July 2026 on why exchange loss projections deteriorated, Chief Financial Officer Mike Marks detailed the specific modeling breakdown: internal underwriting had assumed that 80% to 85% of individuals losing subsidized coverage would become uninsured, whereas the actual migration was nearly one-for-one8. That post-mortem reflects an executive team that monitors its operational assumptions closely. The critical question for investors is whether leadership's underwriting for 2027 and 2028—when federal Medicaid payment cuts take effect—will prove more resilient.
Weighing the Case
Weighing these countervailing arguments reveals a clear demarcation: the bull case relies on demographic volume, operational execution, and aggressive capital return, while the bear case centers on statutory policy risk. Operating data through mid-2026 demonstrates that underlying demand across HCA's hospital network remains intact, as evidenced by positive same-facility admission growth1. Simultaneously, the year's disclosures proved that federal policy shifts can erase more than $1 billion from Adjusted EBITDA in a single fiscal cycle8. Following that revision, management recalibrated its 2026 financial expectations to an earnings run rate consistent with its historical long-term Adjusted EBITDA growth target of 4% to 6%8.
That recalibration leaves HCA with a more demanding investment equation: an elite, disciplined hospital operator with organic volume tailwinds, navigating a multi-year regulatory squeeze on its primary profit pools. The core investment question is whether internal operating efficiencies and leveraged share repurchases can compound per-share earnings faster than federal policy compresses the aggregate margin base.
The 3 KPIs That Matter Most
-
Same-facility equivalent admissions growth. This metric provides the cleanest indicator of underlying organic demand across both inpatient hospital beds and outpatient ambulatory sites. Management's long-term baseline target remains 2% to 3% annual growth21.
-
Contract labor as a share of salaries, wages and benefits. This line serves as the primary leading indicator of clinical labor stress. Having normalized from peak pandemic disruptions, management views a run rate of approximately 4.2% as its sustainable operational baseline21.
-
Same-facility revenue per equivalent admission. Combining commercial managed-care pricing power, case-mix acuity, and government reimbursement formulas into a single unit metric, this indicator serves as the financial fault line where statutory payment cuts and private contract renegotiations appear first.
The remaining question is what milestones and strategic inflection points will determine whether operational discipline or regulatory attrition dictates the terminal outcome.
XII. Epilogue & The Forward Watchlist (10–15 min)
The Summary Judgment
Back in Nashville, the building that anchors HCA's corporate campus sits a short drive from the site of the former Park View Hospital. The geographic distance is small; the institutional journey is vast. Over nearly six decades, a physician-founded hospital management venture evolved into an aggressive corporate roll-up, the target of a historic federal fraud settlement, a landmark private-equity leveraged buyout, and ultimately one of the most durable capital compounders in American healthcare.
The operating record supports a clear but bounded conclusion. HCA is an exceptionally disciplined operator of dense local hospital networks, and its systematic share-repurchase engine has turned steady operating earnings into substantial per-share growth. Yet its operating margins remain tethered to a reimbursement system shifting beneath it. Statutory Certificate of Need regimes do not shield its two largest state markets, and its history with ancillary diversification and regional nonprofit acquisitions reveals the operational boundaries of its standardized playbook. The company is neither an insulated regulated utility nor an asset-light technology platform; it is a capital-intensive scale operator directly exposed to statutory policy risk.
The Forward Watchlist
The Mission Health trial. Scheduled for trial in North Carolina, the case will test how courts interpret service-retention covenants in nonprofit hospital acquisitions, establishing legal precedent for whether operational staffing adjustments constitute an impermissible discontinuance of care and shaping the contractual terms of future health-system transactions926.
Exchange and Medicaid policy. Key developments to monitor include whether individual exchange enrollment stabilizes after the 2026 subsidy expiration, how state legislatures respond to the federal provider-tax freeze taking effect in October 2026, and how executive management quantifies the net earnings headwind from scheduled 10-percentage-point annual reductions to grandfathered directed payments beginning in 202828.
Resiliency and artificial intelligence. Executive leadership is relying on enterprise resiliency programs—integrating artificial intelligence across revenue-cycle management and supply-chain logistics alongside centralized shared services—to bend the hospital cost curve218. The critical benchmark for investors will be whether same-facility operating expense per equivalent admission continues to hold flat against underlying wage and supply inflation.
Capital allocation balance. Management plans to execute the majority of its remaining share-repurchase authorization during 2026 while concurrently deploying more than $7 billion in capital expenditures across inpatient beds and outpatient facilities over a three-year horizon8. The ongoing balance among share repurchases, total balance-sheet leverage, and capital reinvestment will reveal how management navigates near-term policy pressure against long-term network expansion.
The founders' foundational premise still holds: acute-care hospitals capture tangible efficiencies when they share capital, clinical expertise, and centralized administrative infrastructure. What HCA's next chapter will determine is whether operational scale and local market density are sufficient to defend equity returns when the statutory rules of American healthcare financing are being rewritten.
References
-
HCA Healthcare Reports Second Quarter 2026 Results — HCA Healthcare Investor Relations, 2026-07-24 ↩↩↩↩↩↩↩↩↩↩
-
HCA Healthcare, Inc. Annual Report on Form 10-K for fiscal year 2025 — SEC EDGAR, 2026-02-10 ↩↩↩↩↩↩↩↩↩↩↩↩↩↩↩↩↩↩↩↩↩↩↩↩↩↩↩↩↩↩↩↩↩↩↩↩↩↩↩↩↩↩↩↩↩↩
-
HCA Healthcare Reports Fourth Quarter 2025 Results and Provides 2026 Guidance — HCA Healthcare Investor Relations, 2026-01-27 ↩↩↩↩↩↩↩↩↩↩
-
HCA to pay $631 million in civil penalties and damages; total recoveries exceed $1.7 billion — U.S. Department of Justice, 2003-06-26 ↩↩↩↩↩
-
HCA Completes Merger With Private Investor Group — HCA Investor Relations, 2006-11-17 ↩↩↩↩↩
-
HCA Announces Pricing of its Initial Public Offering — HCA Investor Relations, 2011-03 ↩↩↩↩
-
HCA Holdings, Inc. Fourth Quarter and Full Year 2011 Results (Form 8-K, Exhibit 99.1) — SEC EDGAR, 2012-02 ↩↩↩↩↩↩↩↩↩
-
Earnings call transcript: HCA beats Q2 2026 estimates — Investing.com, 2026-07-24 ↩↩↩↩↩↩↩↩↩↩↩↩↩↩↩↩↩↩↩↩↩↩↩↩↩↩↩↩↩↩↩↩↩↩↩
-
AG Jackson Wins Key Arguments as HCA/Mission Hospital Case Proceeds to Trial — North Carolina Department of Justice, 2026-07-28 ↩↩↩↩↩↩
-
Thomas F. Frist Jr. — Washington University in St. Louis Commencement Archive, 2017 ↩↩↩
-
HCA Healthcare Corporation — Tennessee Encyclopedia ↩↩↩↩↩↩↩↩↩↩↩↩↩
-
Health care giant had beginnings in Tenn. hospital — Business Insurance ↩↩↩
-
Fried chicken, the Colonel, and the Nashville businessman — Winchester Sun, 2021-12-06 ↩↩
-
Hospital Corporation of America — Encyclopedia.com (International Directory of Company Histories) ↩↩↩↩↩↩
-
Columbia/HCA Healthcare Corporation — Encyclopedia.com (International Directory of Company Histories) ↩↩↩↩↩↩↩↩↩↩
-
Rick Scott and the fraud case of Columbia/HCA — PolitiFact, 2010-06-11 ↩↩↩↩↩↩↩
-
HCA Buyout: Bain and KKR's $33 Billion Bet — Wall Street Journal, 2006-07-25 ↩↩
-
Before & After: HCA by the numbers — Fortune, 2011-03-08 ↩↩↩↩
-
HCA Healthcare (HCA) Q4 2025 Earnings Call Transcript — The Motley Fool, 2026-01-27 ↩↩↩↩↩↩↩↩↩↩↩↩↩
-
40 Years of Certificate-of-Need Laws Across America — Mercatus Center ↩↩↩
-
2019 Bill Summaries: CS/HB 21 (Health Care Facilities) — The Florida Senate, 2019 ↩↩↩
-
HCA Healthcare Completes Purchase of Mission Health — HCA Investor Relations, 2019-02-01 ↩↩↩↩
-
Attorney General Josh Stein Sues HCA for Violating Asset Purchase Agreement — North Carolina Department of Justice, 2023-12-14 ↩
-
Judge allows NC attorney general's lawsuit against HCA over Mission Hospital to proceed to trial — BPR News, 2026-07-28 ↩↩↩↩↩
-
North Carolina Superior Court Denies Class Certification In Hospital Monopoly Case — Duane Morris Class Action Defense Blog, 2026-09-17 ↩
-
HCA lowers expectations for the year, citing ongoing labor challenges — Healthcare Dive, 2022-04-22 ↩↩↩↩↩↩
-
HCA Healthcare (HCA) Q3 2023 Earnings Call Transcript — The Motley Fool, 2023-10-24 ↩↩↩↩↩↩↩↩↩↩↩↩↩↩↩↩↩
-
HCA Completes Acquisition of Envision Joint Venture — Healthcare Dealflow, 2024-08 ↩↩↩
-
HCA misses Q3 expectations on costs from staffing firm Valesco — Healthcare Dive, 2023-10-24 ↩↩↩
-
HCA Healthcare Chairman and CEO Milton Johnson to Retire; Current President and COO Sam Hazen to Become CEO — HCA Investor Relations, 2018-09-10 ↩↩↩↩
-
HCA Healthcare Reports Fourth Quarter 2023 Results and announces CFO transition (Form 8-K, Exhibit 99.1) — SEC EDGAR, 2024-01 ↩
-
Schedule 13D filed by Frist-affiliated holders of HCA Healthcare — SEC EDGAR, 2026-02-10 ↩
-
Tenet Healthcare Fourth Quarter and Full Year 2024 Results (Form 8-K, Exhibit 99.1) — SEC EDGAR, 2025-02-12 ↩↩
-
HCA Healthcare Using Algorithm Driven Technology to Detect Sepsis Early and Help Save 8,000 Lives — HCA Investor Relations, 2019-05-16 ↩
 LinkedIn
 WhatsApp
 Reddit
 Hacker News
 Email
 Kindle
 RSS Feed
 Spotify
 Apple Podcasts
 Amazon Music
 Audible
 YouTube