CareTrust REIT, Inc.: The Public Market Flywheel of Healthcare Real Estate
I. Introduction & Episode Roadmap
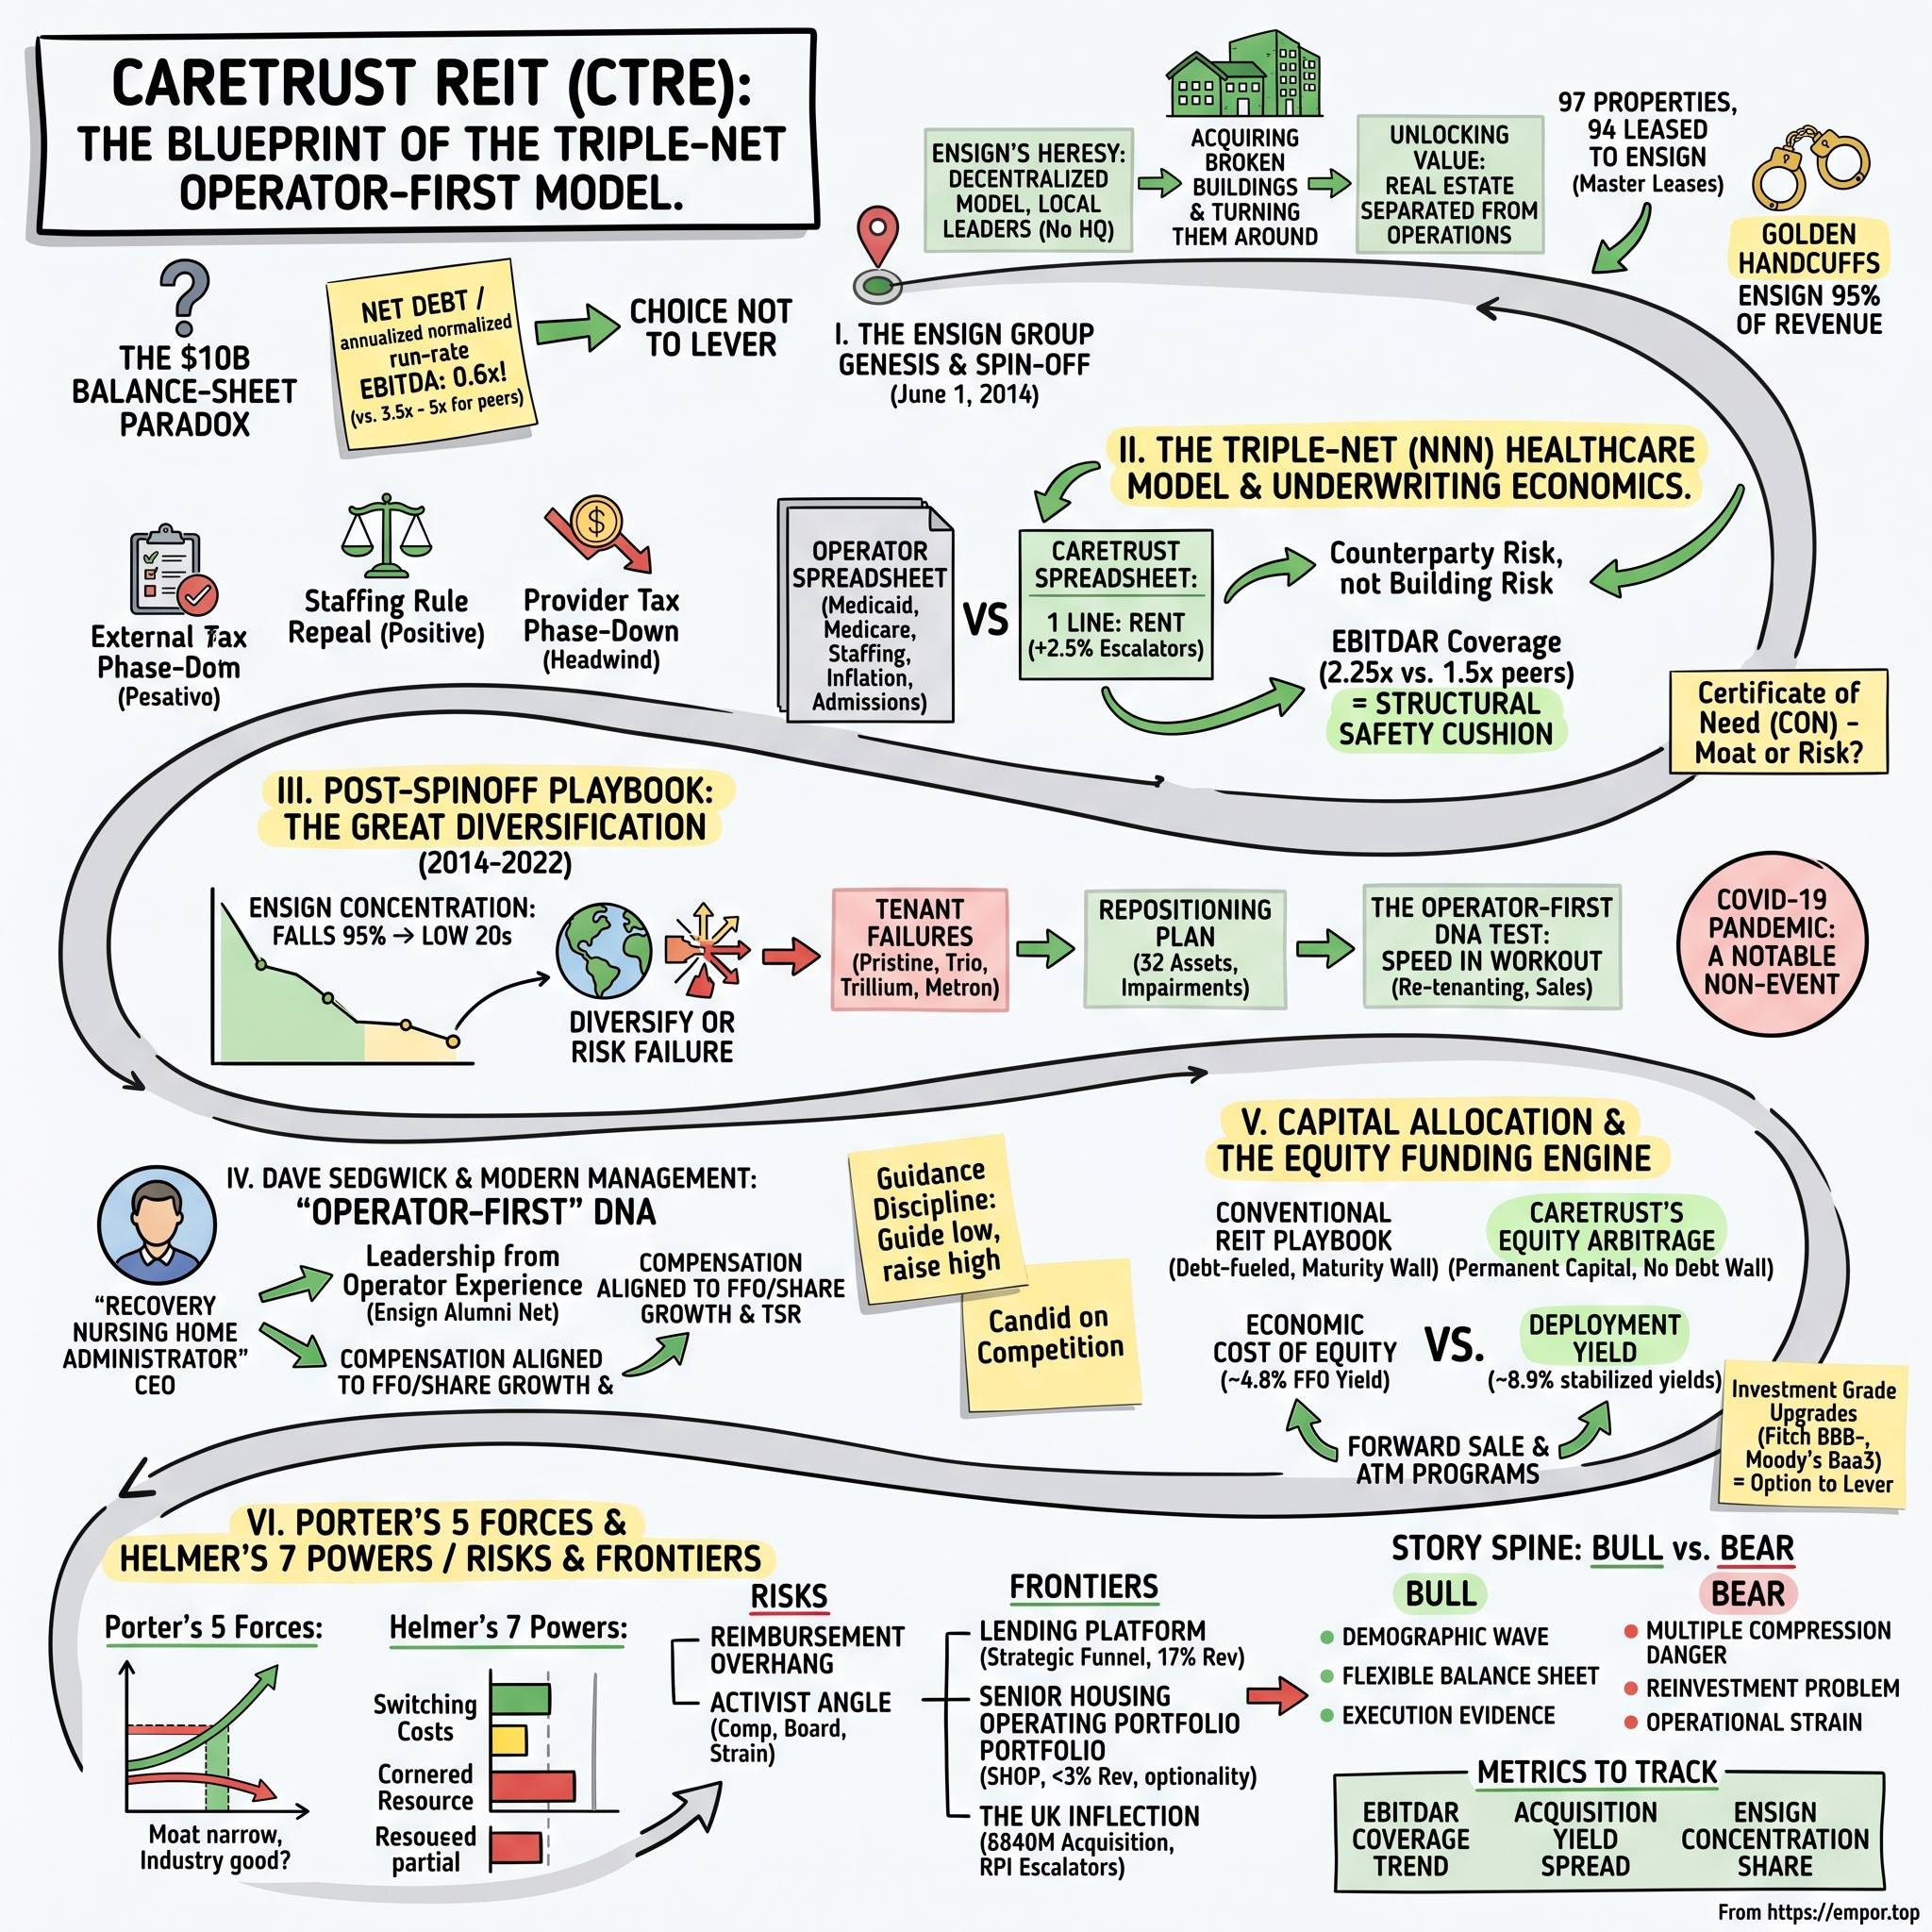
Start with a number that shouldn't be possible. In the summer of 2026, CareTrust REIT is a roughly $10 billion healthcare landlord, one of the fastest-growing property companies in America, buying skilled nursing homes in the United States, care homes in the United Kingdom, and assisted-living communities from Arizona to Texas at a pace that has doubled its rent roll in barely two years. And it is doing all of this while carrying almost no net debt. At the end of the first quarter of 2026, its net-debt-to-EBITDA ratio was 0.6x — a rounding error in an industry where competitors routinely run at five and six times.1 Real estate investment trusts are supposed to be leverage machines. CareTrust is running the engine with the tank nearly empty and somehow going faster than everyone else.
That paradox is the whole story. A REIT, by law, must pay out at least 90% of its taxable income to shareholders, which means it cannot hoard earnings to fund its own growth the way a normal company can. To expand, it has to go back to the capital markets — sell stock, sell bonds — over and over again. The cost of that capital is therefore not a footnote for a REIT; it is the business. And CareTrust has engineered its entire existence around one insight: if the public market values your shares richly enough, you can raise equity cheaply, buy real assets at high yields, and pocket the difference on every deal, forever, without ever touching the debt markets in anger.
Consider how strange this is against the backdrop of the last few years. Between 2022 and 2024, rising interest rates were supposed to be an extinction-level event for REITs. The entire sector runs on borrowed money to buy long-lived assets, and when the cost of that money triples, the math that justifies a building's price simply stops working. Across commercial real estate, deals froze, valuations sagged, and leveraged owners spent the period playing defense — extending maturities, cutting distributions, selling assets to survive. A healthcare landlord dependent on the fragile finances of nursing home operators should have been among the most exposed of all. Instead, CareTrust used those same years to go on the largest buying spree in its history, deploying record capital in back-to-back years precisely while its debt-laden competitors were forced to sit on their hands. Understanding how a company inverted the defining stress of its industry into its greatest opportunity is the puzzle this article sets out to solve.
The company at the center of this is CareTrust REIT, Inc., traded on the New York Stock Exchange under the ticker CTRE, a self-administered, self-managed REIT that leases skilled nursing, rehabilitation, and senior housing properties to operators under triple-net leases. It was not born in a boardroom brainstorm. It was spun out of a single nursing home company in 2014 with one tenant, one source of rent, and a fair amount of skepticism attached. What it became is the subject of this article — told, as always, with an independent eye. CareTrust is a genuinely impressive compounding story, but a large part of that story is a valuation the market has chosen to award it, and valuations are the most reversible thing in finance.
Three themes run through everything that follows. The first is what we'll call the operator lens: CareTrust's management did not come up through investment banking. They came up running actual nursing homes, and that background shapes how they underwrite every building. The second is the cost-of-capital flywheel: the self-reinforcing loop by which a premium stock price funds accretive acquisitions, which grow earnings per share, which support the premium. The third is diversification under way: the deliberate, decade-long project of turning a one-tenant spin-off into a three-engine international consolidator spanning US skilled nursing, UK care homes, and a new senior-housing operating platform. Each theme is also a risk in disguise, and we'll test all three. Let's begin where the company began — inside another company entirely.
 Subscribe on LinkedIn
II. The Genesis: The Ensign Spin-Off (2014)
To understand CareTrust, you have to start with a nursing home operator that most investors have never thought hard about: The Ensign Group. Ensign built itself on a philosophy that sounds almost quaint in an industry dominated by centralized chains — radical decentralization. Each facility administrator was treated less like a middle manager and more like the owner of a local business, free to hire, staff, adjust clinical programs, and answer to the demographics of their own zip code. The theory was that healthcare is intensely local — that the right way to run a nursing home in suburban Texas is not the right way to run one in coastal California — and that the people closest to the patient make the best decisions. Ensign turned that culture into one of the great operating track records in the sector.
But a great operating company sitting on a pile of owned real estate has a structural problem. The stock market wants to value an operator on its growth, its margins, its clinical execution — the asset-light story. It wants to value real estate on stable, bond-like rental cash flows — the asset-heavy story. Bundle the two together and you get a conglomerate discount, where neither half is valued properly. The clean solution is to separate them. So on June 1, 2014, Ensign completed a tax-free spin-off, distributing one share of a brand-new company, CareTrust REIT, to its shareholders for every Ensign share they held.[^4][^5]
The mechanics were straightforward and, in hindsight, elegant. Ensign moved substantially all of its owned real property — roughly 94 net-leased healthcare properties plus a handful of senior-housing assets that CareTrust would operate itself, spread across ten states — into CareTrust, and then leased those buildings right back on long-term, triple-net master leases.[^4][^5] Ensign kept doing what it did best, running facilities. CareTrust collected the rent. The founding CEO was Gregory Stapley, an Ensign co-founder and its longtime general counsel — a lawyer's lawyer who had helped build the company and now would steward its real estate as an independent public entity.[^4]
Here is the part a neutral observer has to sit with, because it was the entire risk of the enterprise on day one: Ensign was 100% of CareTrust's tenant base.[^4] Every dollar of rent, every share of the dividend, depended on the continued health of one operator. This was not a diversified landlord; it was a single-tenant bond with a stock ticker. If Ensign stumbled, CareTrust had no second leg to stand on. The spin-off's promise — independence, the ability to raise capital separately, a clean real-estate multiple — was real, but it came wrapped in a concentration risk that would have made most institutional investors flinch.
It is worth pausing on why a company would voluntarily create a single-tenant bond and hand it to its shareholders, because the logic reveals something about how capital markets reward focus. A spin-off is, at bottom, a bet that two clean stories are worth more than one muddled one. As a division inside Ensign, the real estate was invisible — its stable rental cash flows buried under the operating company's growth narrative, financed on the operator's balance sheet and terms. As an independent REIT, that same real estate could tap the deep, cheap pool of capital that income investors reserve for landlords, and it could do so on its own credit and its own timeline. The spin gave each company its own currency and its own cost of capital. For CareTrust, that access to independent capital was not a nicety; it was the precondition for everything the company would later become. The skepticism was real — a one-tenant REIT is a fragile thing — but the structural prize was a machine that could raise money to buy more buildings, which a division never could.
What made the bet defensible was the thing CareTrust carried out the door along with the buildings: Ensign's DNA. Stapley and his team did not think like typical institutional landlords who evaluate a building by its cap rate and its lease term. They thought like operators. When they looked at a nursing home, they saw the local labor market, the state's Medicaid reimbursement politics, the quality of the clinical management team, the reputation of the building in its community. That operator's eye — the ability to tell a good facility from a good-looking spreadsheet — is the closest thing CareTrust had to a proprietary advantage, and it is the through-line that connects the nervous single-tenant company of 2014 to the confident three-continent consolidator of today. To see why it mattered so much, you have to understand the strange economics of the assets themselves.
III. The Core Engine: Skilled Nursing Economics & The Operator Lens
A skilled nursing facility is not a building in the way an apartment complex is a building. It is a small, heavily regulated hospital-adjacent business whose revenue comes not from tenants writing rent checks but from the government. That single fact reorganizes everything about how the real estate behaves. When you own an office tower, your risk is whether companies want space. When you own a nursing home, your risk is whether Medicare and state Medicaid programs will keep paying, at what rate, under what rules — and whether the operator inside can deliver care well enough to keep the beds full and the regulators satisfied.
The revenue splits into two very different streams. Medicare, the federal program, pays for short-term, post-acute care — the patient recovering from a hip replacement or a stroke who needs a few weeks of rehabilitation before going home. These stays are shorter and pay considerably better, reimbursed on a case-mix-adjusted daily rate.5 Medicaid, the joint federal-state program, pays for long-term custodial care — the frail elderly resident who will live in the facility for years. Medicaid is the dominant payer by volume, and it pays a state-set per-diem rate that is widely documented to sit at or below the actual cost of care.5 The art of running a profitable SNF is, in large part, the art of managing this payer mix: attracting enough of the higher-margin Medicare rehab business to subsidize the thin-margin Medicaid base.
It is worth dwelling on why the Medicare stay is the profit center, because it explains the operating skill CareTrust is really underwriting when it picks a tenant. Medicare reimburses skilled nursing under a system that pays more for sicker, higher-acuity patients who need intensive therapy and clinical management — the post-surgical, post-stroke, post-hospitalization cases.5 An operator who can attract that higher-acuity, shorter-stay business, manage the clinical complexity well enough to discharge patients successfully, and keep the beds turning, earns margins the long-term Medicaid census could never produce on its own. This is the "art" of the payer mix, and it is not a spreadsheet skill; it is an operating skill — building referral relationships with local hospitals, staffing the therapy gymnasium, running the clinical program tightly enough to keep readmission rates low so hospitals keep sending patients. A landlord who cannot tell which operators are good at this is flying blind. A landlord staffed by former administrators can look at a building and estimate its Medicare mix the way a restaurateur can estimate a kitchen's throughput by watching the line. That, in concrete terms, is what the operator lens buys.
Now overlay the supply side, and you find something that looks a lot like a moat. In roughly 35 states, "Certificate of Need" laws require a provider to obtain state permission before adding nursing beds or building a new facility.6 You cannot simply decide to open a competing nursing home across the street; the state has to agree that the community needs the beds. For an owner of existing, licensed, well-located facilities, that regulatory friction is a gift — it caps new supply and protects the value of the beds already in the ground. It is a genuine structural advantage, though a neutral analyst should note it is also a political artifact that legislatures periodically threaten to repeal.
Into this environment CareTrust brings the triple-net lease, and it is worth being precise about what that means because it is the source of the company's cash-flow stability. Under a triple-net (or "NNN") lease, the operator — not CareTrust — pays essentially every cost of occupying the building: the property taxes, the building insurance, the maintenance, the capital expenditure on the roof and the HVAC and the structure.5 CareTrust's leases typically run long, with annual rent escalators tied to inflation — in its 2026 guidance the company assumed 2.5% inflation-based bumps — so the rent grows a little each year with almost no corresponding cost to the landlord.3 The result is a remarkably clean stream of income: CareTrust collects a rent check and passes the operational headaches to the tenant. In the first quarter of 2026 it collected 100% of contractual rent and interest.3
The metric that tells you whether that rent is safe is EBITDARM coverage — earnings before interest, taxes, depreciation, amortization, rent, and management fees, divided by the rent the operator owes. It answers a simple question: for every dollar of rent due, how many dollars of cushion does the operator generate before rent? A new skilled-nursing lease is often underwritten to roughly 1.3 times. CareTrust's stabilized triple-net portfolio, as of the most recent trailing-twelve-month disclosure, ran at 2.79x EBITDARM coverage overall — with the skilled-nursing piece at 3.14x — and 2.25x on the tighter EBITDAR basis.13 Those are unusually strong numbers, and they are the quantitative fingerprint of the operator lens: pick better operators, and your rent is better protected.
There is a second, less obvious tool CareTrust has used to widen its funnel of deals, and it is worth understanding because it looks confusing on the balance sheet: lending. Several years ago the company began making loans to operators — but with a rule attached, one management repeats almost as a mantra. It will only lend when the loan either comes packaged with a real-estate acquisition or, in management's judgment, will lead to one.3 A loan, in other words, is a relationship-builder and an option on a future purchase, not a yield play. The wrinkle is accounting: when a sale-leaseback carries a tenant purchase option far enough out — nine or ten years — the accountants may require CareTrust to book the whole transaction as a "financing receivable" rather than as owned real estate, even though management thinks of it, and structures it, as a lease.3 The practical effect is that CareTrust's reported loan book looks larger and its real-estate book smaller than the economic reality. For a neutral analyst this is a reminder to read past the labels: a growing "loan" line here is often just owned real estate wearing an accountant's disguise, and the strategy's real purpose is to seed the off-market pipeline that increasingly defines the skilled-nursing market.
Where does CareTrust sit in the competitive food chain? The gorilla is Omega Healthcare Investors, the long-established skilled-nursing REIT, worth roughly $15 billion in mid-2026.20 Below it sits Sabra Health Care REIT at around $5.5 billion, with National Health Investors and LTC Properties smaller still.20 CareTrust, which came public as a roughly $1 billion afterthought in 2014, had by the summer of 2026 grown to about $10 billion in market value — leapfrogging Sabra and closing the gap on Omega's long-held premium status.20 Remarkably, CareTrust is now worth about as much as Ensign, the parent that birthed it.20
The tenant roster underneath that growth tells the diversification story in miniature. Ensign remains the anchor at 21% of revenue, still the crown jewel.1 PACS Group, a newer publicly traded operator running a decentralized playbook of its own, is second at 10% — a name we will return to, because it has become the sharpest thorn in the bull case.1 Then a tier of strong regional operators: Priority Management Group at 8%, the UK's Minster Care Management at 6%, Links Healthcare and MFA at 5% each.1 CareTrust's stated preference is for these regional "local heroes" over sprawling national chains, on the theory — very much an operator's theory — that a focused operator who knows their markets defaults less often than a debt-laden giant stretched across forty states. That preference is a bet on human judgment. The next section is about the financial machine that makes the bet pay.
IV. The "Virtual Flywheel": Cost of Capital Advantage & The Fortress Balance Sheet
Here is a thought experiment that gets to the heart of CareTrust. Suppose you run a company legally required to hand almost all your profits to shareholders every year. You cannot save up for growth. Every acquisition you make must be funded by fresh capital raised from outside. Now suppose the stock market, for reasons of your track record and your reputation, values your shares so highly that when you issue a new share, the cash you receive costs you very little in terms of future earnings you give away. And suppose the assets you buy with that cash throw off high yields. You have just described a money machine — and you have described the mechanism CareTrust has spent a decade perfecting.
The engine has a name in REIT circles: accretive spread investing. It works like this. CareTrust issues equity when its stock is expensive relative to the private-market value of the buildings it owns — that is, when it trades at a premium to its net asset value. It then takes that cheaply raised money and buys nursing homes and care homes at high going-in yields. In the first quarter of 2026 the company invested at a blended stabilized yield of roughly 8.8%, and across the first four-plus months of the year it deployed about $1.1 billion at approximately 8.9%.3 The gap between the low cost of the equity and the high yield on the assets flows straight into funds from operations per share. Do this deal after deal, year after year, and earnings per share compound while leverage stays flat. That is the flywheel: growth funded by valuation, valuation supported by growth.
The tool that makes the machine hum without spilling capital is the at-the-market equity program with forward sale agreements — an unglamorous piece of financial plumbing that deserves a plain-English explanation. A traditional secondary stock offering is a blunt instrument: you dump a big block of new shares on the market at once, often at a discount, and you're sitting on the cash before you have anything to spend it on, which drags down your returns. An ATM program instead lets a company dribble shares into the market gradually at prevailing prices. The forward feature adds the clever twist: CareTrust can lock in today's share price by agreeing to sell shares later, deferring the actual issuance and the receipt of cash until the day an acquisition closes.7 The company effectively pre-sells its equity at a good price but only pulls the trigger when it needs the money — eliminating the "cash drag" of unproductive money sitting idle. In the first quarter of 2026 alone, CareTrust settled $129.5 million of gross proceeds under this forward program in support of its buying spree.3
Now the fortress part. While peers operate at five to six times net debt to EBITDA — a level that makes them acutely sensitive to interest rates — CareTrust ended the first quarter of 2026 at that 0.6 times figure, and net debt was a trivial share of enterprise value.13 Management's own long-term target leverage range is 4x to 5x, which means CareTrust is running roughly an order of magnitude below where it has told investors it is willing to go.3 It has no scheduled debt maturities before 2028.3 This is not caution for caution's sake; it is a strategic weapon. When the Federal Reserve raised rates sharply and the cost of debt spiked for the whole industry, leveraged competitors saw their acquisition math break and pulled back. CareTrust, funding itself with equity rather than debt, simply kept buying — often from distressed or motivated sellers at attractive yields, while rivals sat on the sidelines.
The flywheel is not, however, a frictionless perpetual-motion machine, and to its credit management has been candid about the moments it slips. In August 2025 CareTrust raised roughly $736 million in a single equity follow-on to pre-fund an unusually large pipeline.12 That gave it enormous firepower, but it also created a timing problem: the cash landed before the deals closed, and for a stretch the company was sitting on unproductive capital while acquisitions lagged — the very "cash drag" the forward program is designed to avoid, briefly reappearing at scale. On the third-quarter 2025 call, the finance team openly named this funding-to-closing gap as a short-term headwind to per-share results.12 It is a small thing, but the willingness to flag a self-inflicted drag rather than paper over it is a data point in management's favor. The same quarter, CareTrust also swapped its $500 million term loan to a fixed all-in rate of about 4.6% for three years — the modest, sensible debt housekeeping of a company that uses leverage sparingly and hedges what little it carries.12
The market has ratified this approach. Fitch upgraded CareTrust to investment grade at BBB- with a stable outlook in May 2025, and Moody's followed with its own investment-grade upgrade around the first quarter of 2026.83 On the Q1 2026 call, CFO Derek Bunker noted that a ten-year bond, if the company chose to issue one, would likely price at a spread of only 130 to 140 basis points — cheap, high-grade debt now available as yet another lever the company has barely pulled.3 The independent observation to make here is subtle but important: a balance sheet this conservative is also, in a sense, under-optimized. CareTrust is leaving return-on-equity on the table by not levering up. Management is trading some near-term return for enormous optionality and safety — a defensible choice, but a choice, and one that only looks brilliant so long as the equity spigot stays cheap.
Because that is the flywheel's hidden dependency. Every turn of it assumes the stock keeps trading at a premium. The moment the market re-rates CareTrust down — for a sector-wide scare, a tenant blow-up, a rotation out of healthcare — the equity gets expensive, the accretive spread narrows or vanishes, and the growth engine stalls. The fortress balance sheet protects against insolvency; it does not protect against a valuation reset. Keep that vulnerability in mind, because it is the axis on which the entire bull-bear debate turns. First, though, the company decided to make the machine bigger by pointing it across an ocean.
V. Going Global: The UK Care REIT plc Acquisition (2025)
By 2025, CareTrust had a good problem and a real one. The good problem was that it was generating capital and deal ideas faster than the US skilled-nursing market could comfortably absorb. The real problem was scarcity: high-quality, off-market American facilities at attractive yields are a finite resource, and CareTrust was competing for them against family offices and private capital that had noticed the same demographics. A company built to deploy capital needs somewhere to deploy it. The answer, when it came, was on the other side of the Atlantic.
On March 11, 2025, CareTrust announced a recommended cash offer for Care REIT plc, a London-listed owner of British care homes formerly known as Impact Healthcare REIT.9 The offer was 108 pence per share — a 32.8% premium to Care REIT's prior close — valuing the equity at roughly $577 million and, with about $240 million of assumed net debt, implying a total transaction value of approximately $817 million.9 The deal closed on May 12, 2025 via a UK court-sanctioned scheme of arrangement; because sterling had moved against the dollar in the interim, the total consideration at completion came in a touch higher, around $840 million.10 With one stroke, CareTrust added 132 care homes and roughly 7,500 beds, plus two facilities leased to the National Health Service, across England, Scotland, and Northern Ireland.10
What did CareTrust actually buy, strategically? Two things. First, a portfolio with a very long runway of contracted rent — the UK leases carried a weighted-average remaining term north of twenty years — and coverage characteristics that management described as exceptionally strong for what are, in substance, senior-housing assets.10 On the Q1 2026 call, Sedgwick noted that where US triple-net seniors-housing deals historically penciled at coverage around 1.1x, the inherited UK portfolio was running closer to 1.75x to 1.8x, and above 2.0x on an EBITDA basis — an unusually thick cushion for the asset type.3 Second, and more subtly, CareTrust bought a growth platform. Care REIT had been capital-starved as a small UK-listed company; bolted onto CareTrust's balance sheet and cost of capital, its dormant acquisition pipeline came alive almost immediately.
Did they overpay? The honest answer is that it is too early to know, but the early evidence is encouraging on management's terms. The company funded the deal through its premium-valued equity and has since been adding British care homes at yields in the mid-8% range — right in line with its domestic hurdle rate.3 In effect, CareTrust exported its US valuation advantage to a fragmented, under-consolidated UK market with favorable demographics: a rapidly aging, structurally under-bedded population served by a cottage industry of small operators. On the one-year anniversary of closing, Sedgwick said the acquired portfolio was performing ahead of expectations in most respects, and singled out the inherited London-based team — its acceptance of CareTrust's culture and its ability to source deals — as the real prize.3
The proof that CareTrust bought a platform and not just a portfolio showed up in the deal cadence. Care REIT had been effectively frozen, unable to grow for years because it lacked access to cheap capital as a small standalone. Within months of closing, CareTrust had a London team sourcing follow-on acquisitions, and by late 2025 the UK represented roughly a third of the company's total investment pipeline — a segment that barely existed as a going concern before the deal.12 Through the first part of 2026 the company closed on additional care homes across the country, and management described the British pipeline as running ahead of the schedule it had set for itself, with more than half of the near-term pipeline concentrated there at one point.3 The strategic logic is consolidation: the UK care-home market is fragmented across small operators, its aging population is under-bedded, and no domestic buyer commands CareTrust's cost of capital. That is the same set of conditions that made US skilled nursing such fertile ground a decade earlier — a fragmented industry meeting a disciplined, cheaply financed consolidator — transplanted to a new country.
The operator lens crossed the Atlantic intact. The new British partners — Minster Care Management, now about 6% of total rent, and Welford at roughly 3% — were selected under the same "by operators, for operators" philosophy that governs the US book, adapted to Britain's local-authority funding model, which differs meaningfully from American Medicaid.113 A neutral note of caution belongs here: coverage on the UK book ticked down modestly in the quarters after closing, which management attributed to idiosyncratic, not thematic, factors — the kind of claim worth watching rather than accepting at face value.12 International expansion also imports currency risk and integration risk, and CareTrust's answer on the former has been to keep new debt dollar-denominated while its sterling rents provide a partial natural hedge.3 The UK move was the second growth engine. The third would take CareTrust somewhere philosophically riskier: into the business of actually operating.
VI. The SHOP Option: Real Operational Optionality (Late 2025–Today)
For its entire life, CareTrust had been a landlord and nothing but a landlord. It collected rent and let operators absorb the volatility of the business inside the walls. In late 2025, it deliberately broke that rule. In early December, the company announced its entry into a Senior Housing Operating Portfolio — SHOP — acquiring three senior-living communities and, for the first time, taking on the operational upside and downside of the buildings itself.13 Management framed it as bolting on a third engine of growth alongside US skilled nursing and UK care homes.
The structural difference is fundamental, and it hinges on a piece of tax law worth unpacking. Under a triple-net lease, CareTrust's outcome is fixed: it gets its rent whether the operator has a banner year or a mediocre one, and it captures none of the upside if room rates soar. Under the SHOP model — enabled by the RIDEA structure, a provision of REIT tax rules that lets a REIT participate in the operating income of a healthcare property rather than just collect rent — CareTrust owns the real estate and hires a third-party manager to run the community for a fee, in this case Sinceri Senior Living.13 The revenue and the operating expenses flow through to CareTrust directly. It is no longer clipping a coupon; it is running a business, with a professional operator on a management contract doing the day-to-day.
Why take on that volatility voluntarily? Because a fixed rent check is a terrible way to capture a boom. Senior housing occupancy was gutted during the pandemic — the national occupancy rate for senior housing fell to a record low near 77.8% in 2021 — and has been climbing back for years, reaching roughly 88.7% by late 2025, above pre-pandemic levels, even as new construction has run far below what the aging population will require.19 In a recovery like that, with room rates rising and occupancy filling, a triple-net landlord captures only its contractual 2.5% escalator. A SHOP owner captures the full margin expansion. It is, in essence, a leveraged bet on the senior-housing demand curve and an inflation hedge that a fixed lease structurally cannot provide.
But a neutral scorecard has to size this correctly, and management itself has been careful not to oversell it. As of the first quarter of 2026, SHOP was tiny — a few communities out of a portfolio of 588 properties and more than 54,000 beds and units.12 Skilled nursing still anchors the business and drives the overwhelming majority of cash flow.1 SHOP is real operational optionality and strategic to the core, not a speculative pivot. And CareTrust has been visibly disciplined about it: on the Q1 2026 call, Sedgwick admitted that competitors with worse costs of capital had been out-bidding CareTrust on SHOP deals through aggressive underwriting, and that the company's willingness to walk away — precisely because it is not forced to deploy into any single engine — was its edge.3 Cap rates in SHOP had compressed 50 basis points or more in six months, with class-A assets in primary markets carrying a "five handle."3 CareTrust's stated target is a low-double-digit internal rate of return, achieved by matching the right regional operator to the right building rather than chasing volume.3
The character of the early SHOP deals reveals the underwriting philosophy. Take the second SHOP investment CareTrust closed, an assisted-living community of roughly 110 units in Prescott, Arizona.3 It was not a distressed turnaround or a lease-up gamble; it was a stable, already-occupied building bought with an existing operator CareTrust had courted for years and a seller it had done repeat business with, priced to a going-in yield in the 8% range and a path to that low-double-digit IRR through modest operational tweaks rather than heroics.3 That is a telling choice: given the freedom to swing for value-add upside, management instead bought stability first and is building the muscle before it stretches. To support the effort, CareTrust has been investing behind the scenes — hiring senior investment and asset-management talent and, notably, building out a data-science function intended to make the company a genuine value-add partner to the managers running its SHOP buildings, not merely a passive owner.12 In a business where the REIT now shares in operating outcomes, better data on occupancy, labor, and rate is not overhead; it is edge.
The candid version of the SHOP story, then, is this: it is the segment with the most upside per dollar and the most ways to go wrong. It imports labor risk, occupancy risk, and expense volatility into what had been a pristine, predictable cash-flow profile — the very stability that earned CareTrust its premium in the first place. Management is entering slowly and on its own terms, which is the right instinct. Whether the discipline holds as the segment scales is one of the genuine open questions of the next few years. With all three engines now running, it is worth stepping back to ask what, if anything, structurally protects this machine from competition.
VII. The Playbook: Corporate Strategy & Hamilton Helmer's 7 Powers
Every compounding story eventually invites the same skeptical question: what stops someone else from simply copying this? Anyone can, in principle, form a REIT, raise money, and buy nursing homes. So we should run CareTrust through a disciplined framework — Hamilton Helmer's 7 Powers, which asks which durable advantages, if any, actually protect a business's economics. The exercise is clarifying precisely because it separates what CareTrust has from what it merely claims.
The strongest genuine power is scale economies expressed through cost of capital. This is the flywheel restated as a competitive weapon. Because the market awards CareTrust a low cost of equity, it can pay more for a given building than a leveraged private-equity buyer or a smaller peer and still have the deal be accretive to its own per-share earnings. That is a real, quantifiable edge in a bidding contest — but a neutral analyst must flag that it is a market-granted power, not a structural one. It exists only as long as the valuation premium exists. Unlike a network effect or a patent, it can evaporate without CareTrust doing anything wrong, purely because sentiment shifts. It is the most important power on the list and the least permanent.
The second is closer to a genuine cornered resource: the sourcing network that flows from the Ensign heritage and the operator lens. A meaningful share of CareTrust's deals are off-market, brought to it because operators specifically want CareTrust as their landlord — they trust that a team of former nursing-home administrators understands their business, will structure creatively, and will be a rational partner when a facility hits a rough patch.3 On the Q1 2026 call, management described the US skilled-nursing market as now predominantly off-market and relationship-driven, the kind of environment where a two-decade Rolodex is hard to replicate quickly.3 This is a real advantage, though it is embodied in relationships and reputation rather than anything contractual, which makes it powerful but not permanent.
The third power is high switching costs, and here the master lease is the mechanism. When an operator leases a dozen facilities from CareTrust, those buildings are typically bundled under a single master lease with cross-default provisions — an all-or-nothing structure.5 The operator cannot cherry-pick, keeping the eight profitable buildings and handing back the two money-losers; a default on any facility is a default on all of them, backed by a corporate guarantee. This structurally insulates CareTrust from localized facility failures and makes leaving prohibitively costly for a tenant. It is the most contractually durable of the three powers, though it protects against individual-building risk, not against a whole operator going down.
Run the same portfolio through Michael Porter's five forces and the picture sharpens into one dominant structural feature: the bargaining power of the buyer. In this industry the ultimate customer is not the resident or even the operator — it is the government, through Medicare and Medicaid, and its bargaining power is close to absolute. It sets the rates, it changes the rules, and no operator or landlord can negotiate with it. That single force overwhelms the others. The threat of new entrants is genuinely low, held down by Certificate-of-Need barriers and the specialized operating skill required. The threat of substitutes is modest — home health and assisted living nibble at the edges of skilled nursing, but the highest-acuity post-acute care has no cheap replacement. Rivalry among landlords is real but civilized, competed on cost of capital and relationships rather than price wars. And the operators, as the direct "suppliers" of tenancy to CareTrust, hold moderate power that the master lease is specifically engineered to blunt. The net read is an industry with attractive entry barriers and durable demand, permanently overhung by a single, non-negotiable payer. That is why coverage cushion matters so much: it is the only buffer against the one force in the system that no amount of financial engineering can control.
What CareTrust does not obviously have is worth naming too, in the interest of neutrality. It has no branding power that reaches the end customer — a family choosing a nursing home has never heard of CareTrust. It has no network effect in the classic sense, no proprietary technology moat, and no counter-positioning that rivals can't imitate. Its real estate is high-quality but not irreplaceable. The honest conclusion is that CareTrust's advantages are real but soft: a cost-of-capital edge that depends on sentiment, a sourcing network that depends on relationships, and lease structures that depend on contracts holding up in bankruptcy court. That is a respectable moat, but it is not a fortress in the way the balance sheet is. And a business whose primary edge is its valuation had better have management worth the valuation — which is exactly where the scrutiny should go next.
VIII. Management Audit & Governance Stress Test
Dave Sedgwick likes to call himself a "recovering nursing home administrator," and the line is more than a folksy joke — it is the single most important fact about how CareTrust is run.3 Before he was an executive, Sedgwick spent over a decade inside Ensign's buildings, licensed as a nursing home administrator since 2001, running facilities and later overseeing operations and leadership development.4 He joined CareTrust at the 2014 spin-off as president and chief operating officer, and on January 1, 2022, he succeeded founder Greg Stapley as CEO.4 The significance is that CareTrust's chief executive can walk into a facility his company is about to buy and read it the way a mechanic reads an engine — the staffing patterns, the clinical culture, the tells that separate a good operator from a good story. In an industry where many landlords are financiers first, that is a differentiated seat.
The finance function passed to new hands at the start of 2026. Bill Wagner, CareTrust's chief financial officer since inception, retired, handing the role to Derek Bunker effective January 1, 2026, in a succession announced on September 23, 2025.14 A correction to a widely circulated bit of shorthand is worth making precisely because this is a management audit: Bunker's immediately prior title at CareTrust was Senior Vice President of Strategy and Investor Relations, and he had joined the company only in 2025 specifically to help lead the Care REIT acquisition.14 His earlier chief-investment-officer experience came at The Pennant Group — not at CareTrust, where the sitting chief investment officer is James Callister.14 The distinction matters: Bunker is a relatively recent arrival stepping into the CFO chair, and the smoothness of that handoff is something to watch rather than assume.
The departing CFO deserves more than a passing mention, because continuity at the top of a finance function matters for a company that lives in the capital markets. Bill Wagner had been CareTrust's chief financial officer since its inception in 2014, steering the balance sheet from a single-tenant spin-off to an investment-grade international REIT — and he built the conservative, optionality-first capital structure that is now the company's signature.1214 On his final calls, analysts lined up to thank him for a decade of partnership, and management framed the handoff to Bunker as a deliberate, year-long succession rather than a scramble.12 Whether that carefully managed transition holds under the pressure of the current acquisition pace is, as noted, something to watch rather than assume — but the process itself was handled the way a credible board handles succession: early, publicly, and with overlap.
The culture that Sedgwick presides over is not just a slide in an investor deck. Every year CareTrust hosts an operator conference, gathering representatives from nearly all of its tenants for several days to swap ideas and compare notes.12 It is an unusual thing for a landlord to do — most REITs would no sooner convene their tenants than an office owner would host a retreat for the companies leasing its floors — and it is a physical expression of the "by operators, for operators" identity. In 2026 management went a step further, disclosing an internal study of publicly reported CMS quality outcomes suggesting that skilled-nursing operators leasing from CareTrust delivered measurably better results than sector averages on star ratings, rehospitalization, and successful discharges, at least among facilities under lease for four or more years.3 A neutral reader should treat a company's own study of its own tenants with appropriate caution — it is management's analysis, not an independent audit — but the mere fact that CareTrust frames operator quality as a business metric, rather than treating clinical care as the tenant's problem, is consistent with the operator lens it claims to run on.
On incentive alignment and behavior over time, the record is genuinely strong, and a skeptic should acknowledge it. Management's compensation is tied heavily to normalized FFO-per-share growth and total shareholder return, which structurally discourages the classic REIT sin of growing the asset base for its own sake at the expense of per-share value.3 The execution history backs this up. CareTrust has repeatedly issued conservative guidance and then raised it through the year: in 2026 it lifted its full-year normalized FFO-per-share guidance in May, putting the midpoint about 14.8% above 2025 and nearly 5% above the initial full-year guidance it had set in February.1322 Over the decade, management has cited the second-highest total shareholder return of any REIT.12 That is a pattern of under-promising and over-delivering, and it is the kind of behavioral consistency that earns the benefit of the doubt.
The clearest evidence of managerial discipline, though, is the diversification march. Reducing dependence on your former parent — while staying on warm enough terms to keep doing business with them — is a delicate act, and CareTrust has executed it steadily: Ensign fell from 100% of rent at the 2014 spin, to roughly 40% by 2018, to 21% by the first quarter of 2026, all without a public rupture in the relationship.[^4]211 Ensign remains the anchor tenant and the highest-quality operator in the book; CareTrust simply stopped being hostage to it. That is capital allocation and relationship management working in tandem.
A governance stress test should still leave a few flags planted. The company is lean, which is efficient but concentrates a great deal on a small leadership group. General and administrative expense has been rising as the company builds out staff for SHOP and the UK — management has framed this as necessary investment, and on the Q1 2026 call attributed part of the increase to hitting incentive targets, a benign explanation that nonetheless bears monitoring.3 And the sheer velocity of acquisitions — more than a billion dollars deployed in the first third of 2026 alone — puts enormous weight on the accounting and asset-management functions to integrate cleanly.3 Fast growth is where control weaknesses hide. So far the evidence is of a disciplined, credible team; the job of a neutral observer is to keep asking whether that holds under strain. And strain, in this business, tends to arrive from the outside.
IX. Risk Radar & Activist/Skeptical Investor Stress Test
The most instructive way to pressure-test CareTrust is to stop admiring the flywheel and start looking for what could jam it. The risks worth taking seriously are not generic macro worries; they are specific to the mechanics of this business, and they cluster in three places: labor, regulation, and the tenant book.
Labor is the ground-level risk, because it is the single largest cost inside every operator's building. The nursing shortage that gripped the sector during and after the pandemic drove up wages and agency-staffing costs, and any renewed spike compresses operator margins directly — which is to say, it eats into the EBITDARM cushion that protects CareTrust's rent. The most feared regulatory version of this risk was the federal minimum-staffing mandate. In April 2024, CMS finalized a rule requiring a registered nurse on-site 24 hours a day, seven days a week, plus minimum nurse-hours per resident day — a mandate operators warned was unfundable given the nurses simply don't exist in many rural markets. That rule has since been dismantled from three directions: a federal court in Texas vacated its core provisions in April 2025, holding CMS had exceeded its statutory authority; the reconciliation law signed in July 2025 imposed a ten-year moratorium blocking enforcement through 2034; and CMS formally repealed the requirement in December 2025.1718 For now, the sword has been sheathed — but labor economics, not the regulation, remain the durable pressure, and the political fight over staffing standards is the kind that returns.
The second risk is the "stroke-of-the-pen" problem endemic to any business dependent on government reimbursement. A change in how Medicare calculates its rates, or a state deciding to squeeze its Medicaid budget, can impair operator profitability overnight, with no negotiation and no appeal. CareTrust does not control this and cannot hedge it; it can only mitigate it by choosing operators with enough coverage cushion to absorb a bad rate cycle. The third risk is the one CareTrust chose to take on: SHOP margin volatility, discussed earlier, which trades the stability of a rent check for direct exposure to occupancy and operating costs.
Now the activist's turn, because the sharpest version of the bear case deserves to be stated at full strength. It goes like this: CareTrust is, at its core, a leveraged bet on a valuation premium and on a handful of tenants. Strip away the flywheel and you have a landlord whose two largest tenants together are nearly a third of its rent, trading at a multiple that assumes nothing ever goes wrong. If the premium compresses, the entire acquisition engine — which is most of the growth story — simply freezes. And this is not hypothetical hand-waving, because it already has a live case study: PACS Group.
PACS is CareTrust's second-largest tenant at 10% of revenue, and it has been under serious duress.1 On November 4, 2024, the short-seller Hindenburg Research published a report alleging that PACS had systematically gamed taxpayer-funded healthcare programs; PACS shares fell 28% and CareTrust's own stock slipped in sympathy.15 Days later PACS disclosed a federal investigation, then delayed its SEC filings for multiple periods, secured forbearance from lenders and a listing extension from the NYSE, and ultimately acknowledged overstating revenue by more than $60 million across two quarters tied to improperly recognized Medicare therapy billings — with a Department of Justice inquiry proceeding.16 For a neutral analyst, this is the bear thesis made flesh: CareTrust's rent from PACS kept getting collected, and management pointedly declined to speculate about PACS on its calls, but the episode demonstrated exactly how a single tenant's governance failure can ripple into CareTrust's share price and, potentially, its cash flow.3
The PACS episode is not the only stress the asset-management team has had to absorb, and the others double as evidence for the counter-defense. An earlier watch-list tenant, Covenant Care, had drawn nervous questions from investors as its coverage tightened and its private-equity backer looked to sell. Rather than wait to be handed back keys, CareTrust got proactive: it involved itself in the operator's transition and moved the facilities to stronger, more committed operators without a disruption to operations or rent collection.12 The company handled a similar transition of buildings away from a struggling operator to a better-credited regional player in 2025, again without missing a beat on rent.12 These are unglamorous, real demonstrations of the one capability that ultimately backstops a triple-net landlord: the ability to re-tenant a troubled portfolio before it becomes a hole in the income statement. That the team came up running facilities, not spreadsheets, is precisely what lets it do this — it can evaluate replacement operators on operational merit and, in extremis, step in itself.
CareTrust's counter-defense is real and worth crediting. The tenant base is genuinely more diversified than it was — PACS at 10%, Priority at 8%, the UK operators building a fourth pillar — so no single failure is existential.1 More importantly, the fortress balance sheet is the ultimate backstop: with net leverage near zero, CareTrust could re-tenant a troubled portfolio, or even temporarily operate facilities itself, without tripping a single debt covenant. Its asset-management team has already demonstrated this muscle, transitioning a struggling operator's buildings to stronger hands without a disruption in rent.12 The defense holds. But the PACS saga is the clearest possible reminder that CareTrust's greatest vulnerability is not its balance sheet — it is the market's willingness to keep paying a premium for a business whose fortunes are tied to operators it does not control. That tension is the whole investment debate, and it deserves a formal accounting.
X. The Bull vs. Bear Case & 3 Core KPIs to Watch
Lay the two cases side by side and the CareTrust debate resolves into a single question: is the premium the company enjoys a durable reflection of superior execution, or a cyclical gift that will one day be repriced? Both sides have real evidence, and a neutral reader should hold both in mind rather than pick a team.
Before scoring the two cases, it helps to clear away three consensus narratives that don't survive contact with the evidence. The first myth is that CareTrust is simply a leveraged Ensign proxy — buy the REIT and you're really just buying a slice of Ensign. That was literally true in 2014 and is materially false in 2026: Ensign is down to 21% of rent, and the company now spans two additional operators above 8%, a British platform, and a nascent operating segment. The dependence is real but partial, and shrinking. The second myth is the inverse: that near-zero leverage means the safest possible REIT with no trade-off. The trade-off is simply hidden. By declining to lever up to even half its stated target, CareTrust is deliberately forgoing return on equity in exchange for optionality and survivability — a rational choice, but a choice that costs current shareholders some compounding, and one that only looks costless because the equity engine has been so cheap. The third myth is that the acquisition machine proves a durable moat. It proves execution, which is not the same thing. The machine runs on a market-granted valuation premium; a moat, properly defined, is what protects you when the market stops being generous. CareTrust has execution and soft powers, not an impregnable structural moat, and the honest bull case has to rest on the former.
The bull case rests on demographics and the capital weapon. The demographic tailwind is not a forecast; it is an actuarial near-certainty. The first baby boomers turned 80 in 2025, and the cohort needing rehabilitation, skilled nursing, and senior housing will swell for two decades while Certificate-of-Need laws and a collapsed construction pipeline keep new bed supply constrained.19 Rising demand against capped supply is the textbook setup for durable pricing power at the operator level, which flows into occupancy, which flows into coverage, which protects CareTrust's rent and supports the assets it buys. Layer on the capital weapon — as long as the stock trades at a premium, CareTrust can consolidate a fragmented US, UK, and senior-housing landscape essentially without debt, compounding per-share earnings deal by deal. Run this through Porter's five forces and the industry structure is favorable: high regulatory barriers to new entrants, limited substitutes for skilled nursing care, and a fragmented operator base that gives a well-capitalized landlord leverage.
The bear case is the mirror image. Its first pillar is the valuation-premium reversal already described: the flywheel runs in reverse if sentiment turns, and there are plenty of triggers — a healthcare-sector rotation, a reimbursement scare, a tenant scandal like PACS writ larger. A landlord whose main advantage is its cost of capital is, uncomfortably, a landlord whose main advantage is its stock price. The second pillar is execution risk in the newer engines: the UK and SHOP are less proven, carry currency and operating exposure, and could drag returns if integration or underwriting disappoints. And underneath both sits the tenant-concentration reality — Ensign and PACS together near a third of rent — which means CareTrust's fate is partly authored by operators whose books it does not keep. Applying Helmer's lens one last time: the powers are real but soft, and the softest of them, cost of capital, is precisely the one the whole growth model leans on hardest.
It is also worth war-gaming the competitive response, because CareTrust's rise has come partly at its peers' expense and they are not standing still. Omega Healthcare, the sector's largest player, has spent years working through its own troubled-operator restructurings and, on the evidence of CareTrust's own commentary, has been exploring the same growth vectors — RIDEA structures, UK expansion — that CareTrust is now pursuing.3 Sabra and the smaller REITs compete for the same off-market skilled-nursing deals, and in senior housing, CareTrust has openly acknowledged being outbid by rivals willing to underwrite more aggressively.3 The competitive question is whether CareTrust's cost-of-capital edge is wide enough and durable enough to keep winning the deals it wants without overpaying. So far the answer has been yes in skilled nursing, where relationships and the operator lens tilt the field, and a more contested "sometimes" in SHOP, where the field is crowded and CareTrust's discipline means walking away often. The strategic risk is not that a competitor copies the model — several are trying — but that the whole peer group bids up asset prices and compresses the very spread that makes the flywheel turn. A rising tide of private and institutional capital chasing the same "silver tsunami" thesis is, paradoxically, the bull case's own worst enemy.
So what should a long-term investor actually watch? Not the noise of quarterly deal announcements, but three specific gauges that reveal whether the machine is still sound:
First, portfolio EBITDARM lease coverage — especially excluding Ensign. Ensign is the strongest operator and flatters the average; the health of the diversified book is the real tell. If coverage across the non-Ensign operators holds near current levels, the rent is safe and underwriting is disciplined. If it drifts down, it signals operator stress arriving before any missed rent does. It is the earliest warning light on the dashboard.1
Second, tenant concentration — Ensign and PACS as a share of rent. This is the diversification thesis in a single number. Continued decline means management is executing the de-risking it has promised for a decade; a stall or reversal — particularly any deepening dependence on a troubled tenant — would undercut the entire "we are no longer an Ensign proxy" argument.1
Third, net debt to EBITDA. This is the integrity check on the whole model. The fortress leverage is what lets CareTrust survive a tenant blow-up and keep buying when others can't. If it stays in the fortress range, the optionality is intact. If it starts creeping toward the stated 4x–5x target, the company is becoming a more ordinary, more rate-sensitive REIT — and the market may value it like one.13
Three gauges, one underlying question: does the premium survive contact with reality? The answer will be written over years, not quarters. Which brings us, finally, to what CareTrust actually is.
XI. Epilogue & Conclusion
The biggest surprise about CareTrust, once you have traced the whole arc, is that its real product was never the real estate. Nursing homes are a commodity that dozens of REITs and thousands of private buyers can purchase. What CareTrust engineered instead was a capital-allocation framework — a disciplined method for converting a public-market valuation premium into private-market yield spreads, deal after deal, without leverage and without drama. The buildings are the raw material. The machine that buys them is the invention.
The durable lesson underneath the story is that operations and underwriting must precede financial engineering, not follow it. CareTrust's founders and its current leadership came out of the buildings, not the trading floor, and that sequence — judgment first, capital second — is why the company sidestepped the debt-fueled, toxic restructurings that crippled other healthcare landlords when the pandemic and rising rates arrived together. A REIT run by financiers might have built the same flywheel; it is far less likely to have picked the operators well enough to keep the flywheel from flying apart. The operator lens is not sentiment. It is risk management with a nursing license.
Where CareTrust goes from here is genuinely open, and a neutral close should resist the temptation to predict. It is now a diversified international healthcare landlord with three engines, an investment-grade balance sheet, and a valuation that both funds its growth and forms its single greatest vulnerability. The demographics are on its side; the tenant risks and the premium's fragility are not going away. The company has earned its track record. Whether the next decade compounds like the first will depend on things not yet in evidence — how the UK and SHOP bets mature, whether the tenant book holds through the next reimbursement cycle, and, above all, whether the market keeps paying up for the discipline CareTrust has so far delivered. The flywheel is spinning. The only certainty is that its speed is set by a price the company does not control.
References
-
CareTrust REIT Announces First Quarter 2026 Operating Results; Increases 2026 Guidance — CareTrust REIT, Inc., 2026-05-08 ↩↩↩↩↩↩↩↩↩↩↩↩↩↩↩
-
CareTrust REIT Financial Supplement — First Quarter 2026 — CareTrust REIT, Inc., 2026-05-08 ↩
-
CareTrust REIT, Inc. (CTRE) Q1 2026 Earnings Call Transcript — Seeking Alpha, 2026-05-08 ↩↩↩↩↩↩↩↩↩↩↩↩↩↩↩↩↩↩↩↩↩↩↩↩↩↩↩↩↩↩↩↩↩↩↩
-
CareTrust REIT Announces David Sedgwick to Succeed Greg Stapley as Chief Executive Officer — CareTrust REIT, Inc., 2021-12-10 ↩↩
-
Skilled Nursing Facility Services (Chapter 6), Report to the Congress: Medicare Payment Policy — MedPAC, 2024-03 ↩↩↩↩↩
-
States curb certificate-of-need (CON) laws to boost bed capacity — Healthcare Dive, 2024 ↩
-
CareTrust REIT Receives Investment Grade Rating Upgrade from Fitch Ratings — Business Wire, 2025-05-28 ↩
-
CareTrust REIT, Inc. Announces $817 Million Recommended Cash Acquisition of Care REIT plc — Business Wire, 2025-03-11 ↩↩
-
CareTrust REIT Closes Acquisition of Care REIT plc, Enters UK Market — Business Wire, 2025-05-12 ↩↩↩
-
CareTrust REIT, Inc. Form 10-Q for the Quarterly Period Ended September 30, 2025 — U.S. Securities and Exchange Commission, 2025 ↩
-
CareTrust REIT, Inc. (CTRE) Q3 2025 Earnings Call Transcript — Seeking Alpha, 2025-11-06 ↩↩↩↩↩↩↩↩↩↩↩↩↩
-
CareTrust REIT Enters SHOP; Acquires Three Senior Living Communities — CareTrust REIT, Inc., 2025-12-01 ↩↩
-
CareTrust REIT Announces the Planned Retirement of Bill Wagner and Names Derek Bunker CFO Successor — CareTrust REIT, Inc. / SEC Form 8-K, 2025-09-23 ↩↩↩↩
-
Nursing-Home Operator PACS Tumbles After Hindenburg Short Report — Bloomberg, 2024-11-04 ↩
-
Nursing Home Giant PACS Acknowledges Overstating Revenue by More Than $60M Over Two Quarters — Skilled Nursing News, 2025-06 ↩
-
Federal Court Strikes Down CMS Nursing Home Staffing Mandate — Faegre Drinker, 2025-04 ↩
-
CMS repeals minimum staffing requirements for skilled nursing, long-term care facilities — American Hospital Association, 2025-12-02 ↩
-
Senior Living Occupancy Rate Continues Rising as New Supply Remains Limited — National Investment Center for Seniors Housing & Care (NIC), 2025 ↩↩
-
Omega Healthcare Investors (OHI) Market Capitalization — StockAnalysis, 2026-07-24 ↩↩↩↩
-
CareTrust REIT (CTRE) Q4 2025 Earnings Call Transcript — The Motley Fool, 2026-02-13 ↩
 LinkedIn
 WhatsApp
 Reddit
 Hacker News
 Email
 Kindle
 RSS Feed
 Spotify
 Apple Podcasts
 Amazon Music
 Audible
 YouTube